Skip to content

Breastfeeding Barriers

 Barriers~

Even the word itself is foreboding.

Breastfeeding advocacy, lactivism, promotion are important to combat what is really a public health problem and should be a public health priority.     ~Breastfeeding should simply be the norm.


“Today’s medical community recognizes what their

predecessors knew a century ago—that the
American propensity to shun human milk is
a public health problem and should
be exposed as such.
“Today’s medical community recognizes what their predecessors knew a century ago—that the American propensity to shun human milk is a public health problem and should be exposed as such.” 

American Journal of Public Health | December 2003, Vol 93, No. 12

It should be SIMPLE~

It is one thing to talk or write a lot about breastfeeding advocacy and promotion… but WHAT does that really do to break down the hospital barriers. Even with some good ideas or some well-written  plans & protocols(ie. as recommended by The Academy of Breastfeeding Medicine)…. I’m here to tell you, all that does very little to actually change an individual  health-care professional’s actions. There is a critical void in the practice of appropriate breastfeeding management strategies and breastfeeding support from the health-care arena.

Working with barriers day-in and day-out can really open your eyes to what some of us, as lactation professionals or advocates, are dealing with on a daily basis. Many of us are ill-equipped to attempt to enforce evidence-based management guidelines.  There must be better support from the management of each facility, organization or Health-System. It needs to start at the top…. to say we now have an evidence-based breastfeeding policy is NOT enough. I believe it starts with each individual being responsible and accountable for their own practice. 

Action Taken~ 

I have written about how Breastfeeding was taught to me in nursing school and what our scary hospital policy looked like when I got started in this profession. 

I have written an article published in a local parent  magazine to coincide with 2007 World Breastfeeding Week supporting practices to keep breastfeeding SOFT and SIMPLE. 

I have been working on so many different ways to try to keep it SIMPLE… trying to reduce barriers. I have written countless competencies at work while trying to gently re-educate my co-workers. I have developed several PowerPoint presentations, poster in-services, poster displays etc.. to try to help my fellow staff members AND physicians fully UNDERSTAND the superiority & importance of breastfeeding and the use of correct evidence-based management advice, assistance or feeding plans. I have learned to be gentle and patient in the process….one step at a time.

I want to keep it simple for the mother…I’ve tried to work on a simple bottom-line approach to eliminate any maternal barriers of feeling overwhelmed or confused with too much or conflicting information.  

I don’t want mothers to think they have to “study” to pass the breastfeeding test….to “perform” correctly!

I encounter a variety of moms from vastly different backgrounds. There are huge differences in their own individual breastfeeding expectations and goals. We have a large breastfeeding/bottle feeding combination population at my facility. I’ve struggled to balance quality promotion and proper education to both mother’s AND the staff. I continue to to educate with acceptance of all individual mom’s actions. I have written about my approach and maternal guilt.

I wrote:

Never overestimate a mother’s desire to breastfeed her infant.  

Never underestimate a mother’s desire to breastfeed her infant.  

Listen to the mother; help her define her true desires and goals.

Support the mother, support the mother, and support the mother.

This is what I have learned and how some of my approaches and strategies have evolved over the last 20 years so that moms and staff alike will listen. I have written these same things at work…. They are hearing me now. I have to say that at least they are listening and some are talking the talk. How do I get them to walk the walk? Only a select few truly care to try.  The following is some of what we still deal with…

Continued Problems …. Persistent Barriers ~

  • Getting the baby skin to skin in the birthing or delivery room–very inconsistent
  • Accomplishing the first breastfeeding in the delivery area (I even revised the nursing form to REQUIRE documentation of a reason WHY not breastfed….) Most common reasons..attempted, mom tired or mom declined. I have to wonder how often it’s really encouraged…and are they trying to help?
  • Some staff still thinking they have to give that “test” feed of water
  • Keeping a healthy baby in the nursery for hours under “observation” while nurse gets all adm paperwork done
  • Giving handouts to mom but not talking to her, not listening, not helping
  • Telling or directing mom firmly, like it’s an order… often with incorrect info- “you really need to feed that baby, wake him up every 2 hours no matter what”
  • Inconsistent observation of latch and feeding progress (At least some are really good at this!!)
  • Giving partial bits and pieces of correct info mixed with misinformation and not accompanied with actual assistance…… then reporting to me  “I said just what you taught me, Melissa!” (A challange to gently correct)
  • Keeping babies away from mother’s…esp at night so “she can sleep”
  • Incorrect use of  formula— given for so many many reasons that are most often because of all the problems above…… sometimes mom asks for formula…. but a little detective work, proper evaluation, assistance and education can possibly help avoid the formula
  • Not understanding the unique characteristics and needs of the ‘near term’ infant. 
  • Being understaffed when busy… we always have a mom/baby dyad with some need for frequent breastfeeding evaluation and assistance when we are crazy busy….they often get lost in the shuffle
  • Staff members not helping a mom because they tell them to wait for me… I am a staff nurse with multiple duties who happens to be a lactation professional. 
  • The discharge diaper bag from formula companies. ***SIGH***
  • Doctors giving conflicting out-dated feeding management advice
  • Doctors scheduling the first baby F/U visit for 2 weeks on first time breastfeeding moms
  • Persistent Lack Of Management Support and Enforcement of Exsisting Evidence-Based Policies and Protocols which I feel leads to staff apathy

I have been patient, really patient. I have seen progress…real progress. I feel so frustrated to be still dealing with some of these barriers. It is overwhelming and exhausting.  I haven’t been trying to do everything alone. I have “duplicated” myself several times. Some of those individuals are still here, others move on to other jobs, others become apathetic over time. Then we get new people who look at things differently with comments like… “This is what we did at __blank___ hospital..”

What do you suggest could help with the real change……the implementation process??

How do I get them to walk the walk???

Please comment and make a suggestion…  Do you have a good one I haven’t tried?


Adoption in a Small Town ~ The Agony of Knowing…. Part II 

Part II

Apparently Sarah had been having a lot of headaches and dizzy spells.  She is 19 yrs old now and had graduated high school, was attending the local college and had moved out of Karen’s home to live with her boyfriend, Justin. Sarah possessed a beautiful free spirit and Justin (who was the father of the baby she’d given up for adoption) was her true soul mate. They were still together.  It was easy to see how Sarah and Justin were truly in love.

Sarah went down to a large hospital in Philadelphia and had many diagnostic tests all confirming brain cancer. Her tumor was too big for surgery right away but the doctors were optimistic that after radiation and some chemotherapy, they could do surgery and remove the tumor. So far the other systems tests looked good. Sarah was a fighter and vowed to beat this thing!

During the chemo and radiation, she lost her hair. Justin also shaved his head! This wasn’t so popular back in 84-85. She was surrounded by great support! By the end of 1985, her tumor had shrunk she was able to have the surgery. They got it all…the whole tumor….all the cancer!  Sarah recovered easily, no long term effects, and went into remission!  Life became normal for them again.

My interactions with Karen and Sarah at this time were not as frequent. I had made an occasional supportive call or visit, but wasn’t involved in the whole process.  Karen was often in Philadelphia, sometimes for weeks at a time and I had had a baby. Neither of us were skiing very much over the past 2 years. My sister had gone to Europe on a 6 month trip with her new husband, so she had only stayed in touch with Sarah by the occasional card or call.

When I did see her or Sarah—the birth, the baby, the adoption … none of that was ever mentioned.

In the meantime, I saw Dr. E a lot at the hospital. I would ask about Joey sometimes, she occasionally had a new picture or new stories to share about his life with his parents  in Atlanta .  Dr. E talked about Joey with such love and pride, she had really bonded with him. She told me it was because she had to keep him with her until the adoption paperwork was finished. She thought I had a special interest because I cared for him from the beginning in the hospital and had helped her so much with infant care instructions to go home. She never knew I was friends with the birth family.

Sometime in 1986, about a year after the surgery, Sarah’s symptoms returned. The tumor was back.

Sarah grew sicker and it became apparent that this cancer might get the best of her, she might not beat it this time, might not make it. She went through more chemo, and decided against further surgery.  There were more risks this time; Sarah didn’t want to take them. She wanted to go home with Justin and live as much as she could.

I had become increasingly conflicted. I thought… ‘Sarah might not live, she or Karen might want to know how well that baby boy is doing’….. ‘They may want to see a picture or see the boy before Sarah dies…..’  I was having an overwhelming desire to let this secret out.

I wanted to shout: “I KNOW WHERE THE BABY IS….. I”VE BEEN WATCHING HIM GROW UP!!!! “

I had some misconstrued idea of my role in my head..the secret I knew could impact others greatly….I should tell …..Shouldn’t I????  If it was my daughter, I think I’d want to know.  I’d want to see her with her child before she died.  It was very inappropriate for me to think this– but I couldn’t let go of this idea, this strange notion in my head that Karen may openly question me about it someday—that I may be a source of comfort to her. My outward behavior remained professional, but inside my mind– nestled with the secret– the thought process was spinning on pure raw emotion. Clearly–I was having a hard time being objective in my thought process.

I decided to ask my friend who had adopted 2 kids; without telling the actual story; I gave her a ‘what-if’ …. Theoretical situation. –If someone knew that one of the birth parents of your children was gravely ill with a serious disease and may die….. Would you want to know?? How would you feel??

Her response to me “I’d be scared shitless! I’d be scared the birth families would descend on my life and want visitation. I’d be afraid my children would not understand. If there was serious health information I should know, I’d want the lawyer to tell me but that’s it.”

 I really needed her perspective.  This was not an open adoption after all. I had NO RIGHT to say anything! It was not my place at all. I took a huge step back, soul searched and pushed back all those emotional desires to tell…

I saw Karen, Sarah and Justin with some of the rest of their family at a Ski party. Sarah was vibrant, funny, laughing and having a great time! She had on a crazy hat to hide her scanty hair and it meshed perfectly with her personality.  We had a wonderful day. I felt much more peaceful about knowing.

I got word about a month later that Sarah had taken a turn for the worse, the tumor growth was aggressive and they had already arranged for a hospital bed & help at home…Sarah’s home.. with Justin at her insistence. Justin was the major caregiver.

While this was happening, I ran into Dr.E again at work. I felt uneasy and started to struggle that same raw emotional conflict. I chatted with her casually & asked her again if she had a picture of Joey.…this time I asked if she could spare one for our bulletin board upstairs where we have pictures of a lot of our babies. She thought that was a great idea. [I know it’s wrong, but I was thinking, someday, maybe I can show Karen and say– the adoptive family sent it to us on the unit. I couldn’t let go of the idea.]  Dr. E said “Sure.. great idea, I’ll get one for you!”

Sarah died peacefully in her home a few weeks later.  Her family was devastated despite how “prepared” they’d been. My family was also very upset. My siblings all tried to make it home for the service.  My husband, mom and sisters all went over to Karen’s house the night before the service.  There were a lot of people there.  Karen was pretty strong but at one point she cried “My baby is gone- she’s gone.. I’ve lost her!” I couldn’t imagine her pain, her grief. I cried with her.

It wasn’t about me—but I was suffering in a different way, struggling with what I knew…that a part of Sarah was out there… healthy and alive.  I couldn’t share that with anyone. I cannot tell them. Going home in the car, I ended up alone with my mom and I had to tell her. I blurted out the whole story. I could trust her. I had to have someone help me. She reinforced what I already knew that of course I couldn’t tell.  I felt better just letting it out to someone.

The funeral home was packed. We bypassed the rows of picture and long lines, gave nods to the family up front and found some seats. I sat there with my husband all teary eyed.  I saw a lot of people I knew. There were also a lot of children running about.  I saw what looked like a set of adorable triplets impeccably dressed in their identical brown suits.  One of the triplets climbed up in the chair across from me and got snuggled in towards his mother, and then he popped right back down running after his brothers.

I slowly became more aware of this mother sitting across from me. The boy climbed back up in her lap as she looked up and met my gaze. 

I could not believe what I was seeing! It was Dr. E.!

She said confused “What are you doing here?”

I said crying “Sarah was the daughter of one of my best friends– Karen…..”

She said “I didn’t know you knew her….. all this time… well–this is JOEY!  Oh –that’s why you wanted a picture! Oh Sweetie.”

I fell to my knees in front of her, my hands on her lap sobbing, I could not control my emotions….

Me sobbing “I didn’t know they knew where he was..I didn’t know, I didn’t know..”

By now she was up and leading me down the hall, holding Joey’s hand…..I’m crying:”did Sarah get to see him? Did Karen? Oh –he’s just so precious….”

She realized I didn’t know about any contact at all so she quietly explained that Sarah had opened up the line of communication when she realized the treatments weren’t working and that she and Justin had wanted to see Joey– spend a little time with him. Then she said ..“Come here, I want you to see something.”

She took me into another room, filled with people I didn’t know. She announced to everyone. “This is the nurse I was telling you about who took such good care of Joey in the nursery as a baby!”  I was sobbing still as she introduced me to her brother and his wife the adoptive parents, Joey, and the other 2 boys (I thought were triplets) who were brothers. I had said earlier in the story that Dr. E’s brother and wife (also both physicians) had gotten pregnant after getting Joey but I never knew they also had the good fortune of adopting another child a few months after Joey. The 3 boys were very close in age. The room was filled with Dr.E’s family who had all made the trip from Georgia! There were grandmas, grandpas, aunts, uncles.. all coming to pay their respects to Joey’s birth mother. What a wonderful openminded loving family! They were mostly staying in a room off to the side out of respect to Sarah’s family. What a gift… for Joey, for Karen and her family and what a gift for me.

Only a few people in Sarah’s family knew she had ever had a baby… …that was more than I thought. Those that knew only found out with-in the last few months. They were all very private about it. I found out later that Karen had still not come to terms with Sarah’s adoption choice. Karen was hoping to help her raise the baby when first finding out Sarah was pregnant. She herself hadn’t really visited with Joey It was very hard for her that Joey was even there… There were pictures on the wall of Sarah, Justin and Joey.. but I had bypassed that when we came in…and had not seen them.


Before the service started, my sisters were standing next to me on some steps, and Dr. E walked past with Joey saying he wanted to say hi to everyone again.

The sister who had been Sarah’s friend said: “Who’s that? Is that one of Sarah’s cousins?”       

I hesitated not know what to say at first… and Karen’s mom looked at me–clearly understanding that I knew.    She said: “It’s OK, you can tell her.” Once again, crying, I told my sister the secret I had kept all these years.

 At the end of the service, people went outside to release flower petals or balloons in the wind and say a final goodbye to Sarah.

I stood next to Joey as he released a balloon. Dr E said “Would you like to say something Joey?”

Joey: “I say goodbye to my birth mother and I am happy my birth father is still alive!”

Adoption in a Small Town ~ The Agony of Knowing…. Part I 

Prelude:  My small town in the mid 70’s had one main highway which held the one and only “hotspot”… an older fast food joint called “Burger Chef”.  Our population for the county was at least 75,000 to 100,000 LESS than it is today. (We have well over 125,000 now). We were rather spread out geographically which made this feel more like a small country town.

When a baby would be placed up for adoption, there was to be great secrecy to protect the identity of both the birth mother and the adopting mother.  Before any type of open adoption, before there were several available agencies and when there wasn’t much “red-tape”….  The doctors had a list (The LIST) of names they collected, their patients who were unable to conceive wanting to adopt. Often, if a mom was considering putting her baby up for adoption, she didn’t say anything to anyone until delivery. (Some never had any pre-natal care) The docs would tell them they could handle everything for her and arrange for a lawyer to come talk to her etc… Once the connection was made between birth mother and lawyer, it was all handled very professionally and legally.

Sometimes, in a small town, working in L&D/NSY, you might accidently be aware of where a baby is going… the identity of the adoptive parents.

The first time this happened to me, I had been at a friend’s house at a party, when another friend drove up- rushed out of the car hollering “We’ve got a baby!! We’re getting our baby!!”. We all knew she had been unsuccessful getting pregnant and was on many waiting lists to adopt. We were all SO happy for her. All of us asked: When? Where? Boy/ Girl? Etc…  All she knew was that a baby boy had been born that day at our general hospital (where I worked).  It was a very strange feeling.  I knew I was going to be seeing that baby the next day at work, possibly assigned to either the mom or baby’s care.

The next day I was in the nursery. The birth mother was a shockingly young teen, 14 years old. The baby, born by C/S, was very healthy (about 8 lbs actually) and he had no problems. I didn’t say anything to anybody. The day that the OB office called to arrange for the final discharge, I had answered the phone…I guess my young little self felt the need to be all truthful and honest. I quietly and meekly told the woman on the other end of the line that I knew where this baby was going.

Dead silence

She asked “What did you say?”  Now.. I had to repeat it…. “I know the adoptive parents of this baby.” She made me feel really bad. “How did I find out this info?” She said I could “NEVER tell anyone I knew, I might jeopardize the entire adoption, these records will be sealed”…etc..  So I kept my mouth shut, the little boy grew up peacefully with his adoptive family, the young birth mother even came back to deliver  more children many years later.

Note to self….. Never do THAT again.

Adoption in a Small Town ~ AGONY  Part I

During a particular busy shift in L&D, circa 1982, a young 17 yr. old girl came up from the ER in very active labor.  She was 5 weeks early, 5cm dilated, 100% effaced with bulging membranes and looked to be moving fast.  It took me a few minutes to recognize her name. Sarah Johnston! Sarah Johnston??  I did a double take and looked at her again. Then I realized this girl was the daughter of one of my best friends! Her mom, Karen, was a ski instructor with me. She and I had skied together for years. Karen was older than me but we shared a lot of the same interests and could talk forever while riding the up the T-bar. Sarah was acting like she didn’t recognize me.. I was actually closer in age to Sarah than to Karen. Since both our whole families practically LIVED at that ski area all winter, we spent a lot of time together and Sarah was always hooking up and skiing with my younger sister. She certainly knew me from the ski area.

(I started to think.. maybe Karen doesn’t even KNOW she’s pregnant! ) After her next contraction, I privately whispered to her that I take privacy and confidentiality very seriously and I would NOT tell her mom anything. I then asked her if she would like me to leave the room. She immediately started to cry and said “no–please–   I’m so scared, please stay till my mom gets here.” (Privately I’m thinking… wheeh… Karen knows…) So I stayed with her and coached her until Karen got there. I gave the other nurses a heads up and they covered my other patients.

 Karen was already in tears when she arrived about a half hour later. I greeted her outside of Sarah’s labor room. She also seemed distressed and uncomfortable with my presence.  I quietly said the same things to her I had said earlier to Sarah. Karen said.. “It’s ok that you’re here. I trust you; it’s just that NOBODY in the family knows that Sarah is pregnant. You have to promise NOT to tell your family or anyone in my family! …I am trying so hard to do what Sarah wants… Not to tell anybody.  I only found out she was pregnant 3 weeks ago. She’s even giving the baby up for adoption! This whole thing is breaking my heart! I didn’t even tell my own mother!”  We didn’t have time to talk anymore.

The baby was born and Sarah did not want to see him or hold him. Although he was a good weight of about 5 Lbs, he had some transitional breathing problems. We needed to take him right over to the nursery.

Sarah asked to be transferred to another floor {which we routinely offer to moms placing babies for adoption. They are always told they may come see the baby any time even if they are on another floor}.  I did not see Karen after that. I felt she would come to me if she wished.  I did not want to be intrusive.  I did not talk again to any of my co-workers about my relationship with the family.

003I focused on caring for the precious little baby boy. He needed a sepsis work-up with labs, Chest X-ray and an IV with antibiotics. He was also under an Oxyhood with a little bit of oxygen support. We would observe and monitor these 35 weekers at our small hospital and decide if they needed to be transported to a bigger hospital. This baby was stabilizing and improving rather than deteriorating. He stayed with us.
The next day, when I came into work, one of my most favorite doc’s, an orthopedic surgeon, Dr. E. was in to see the baby. I couldn’t figure out why, what was going on.  She had scrubbed up and was standing at the incubator and asked..”Could I hold him?” I only asked,–are you related to him?  We didn’t have the kind of security then that we do now.. It wasn’t that unusual for another doctor to show interest in a baby, esp a woman doctor.

Dr. E said “I’m kind of related….my brother and his wife are adopting him! So I guess that makes me his Aunt! I’m actually going to keep him with me for a few weeks until the paperwork is signed. My brother lives in Atlanta.” I found out later that this was arranged because of the LIST, that Sarah had not made any plans for agencies and was very eager to allow the doctor’s lawyer to handle all the arrangements.


I saw Sarah and Karen only one more time in the hospital after the birth. They were standing outside the nursery glass. Sarah was being discharged and had asked to stop by the nursery.  I went out and invited them inside to see the baby.  They both came in.. hesitantly.  Karen had tears streaming down her face, trying to be strong for Sarah. Sarah got a little closer; she asked a few questions like a teenager would, and then she wanted to go. She wasn’t acting upset, her affect wasn’t flat; she was just acting pretty normal to me. So they left.  Part of my heart left with Karen. I knew this had to be so hard for her.

The adoptive family had named the baby “Joey”.  Soon all the nurses called him Joey. He stayed with us for a full course of antibiotics, 7 days.  Dr. E came up from her ortho office to see him frequently and she spent a lot of time with him. She asked me so many questions and wanted me to help her with so many aspects of his care. I spent a lot of time with her.. She didn’t have children yet. It was clear to me that she was so in love with this baby! Dr. E didn’t know, but I had a special interest in this baby too! It made me so happy to know Karen’s grandson was going to such a great family.

Over the next several months, Dr. E would occasionally show us pictures of Joey with his family down in Atlanta, how big he was getting etc.. She told me also that once her brother and his wife had adopted Joey, they found out they were pregnant! When Joey was about a year old, he had a little brother!

Some time went on; life was normal…I saw Karen and Sarah all winter long on the slopes and at some family events. Karen would visit at my house like usual. Sarah would visit with my little sister like usual. Nothing was said.  I never told my mother, my husband, my sister or anyone my family. NEVER. I never talked to Karen about it. I respected her privacy and felt if she wants to talk about it, she will.

One day, about 1 ½  years after the birth I ran into Karen at the hospital. She looked very upset.

“Karen.. What’s the matter???”

“It’s Sarah. [crying now] They think she has a brain tumor. We are transferring her to Philadelphia now for tests and maybe even surgery!!”

“Oh my God Karen! “

Stay tuned for Part II

Surprise TWINS !! The Keystone Cops Episode

 twinsOne gorgeous lazy summer day in 1976–  I got the call from the OB office (across the street) about 11 am. 
Office Nurse: [matter of fact voice] “We’re sending over a woman with twins.”

Me: [Calmly] “Ok. Is she is labor? 


Office: [still matter of factly] “She’s in very active labor, Dr. B just checked her and she’s 8cm.”

Me: [A little less calmly] “Whooo.. really??  We don’t have a doctor over here. Make sure Dr. B knows that. We’ll go get things ready. How far along is she?” (in the pregnancy)

Office:“She’s about 8 months maybe 35/36 weeks….. we aren’t quite sure, she just came into town– to the university — and this is actually her first visit”

Me: [Quickly] “Well — Ok- thanks, better get rolling! ”  

We Hang-up

Me- To our group: “Guys- we’ve got twins in active labor coming from office right now- she’s already 8cm!”  

In those days, twins were always expected to be delivered vaginally.. I never even thought to ask  about which pregnancy this was, presentation, (head down? breech?), membranes ruptured?……. not that I had much time to gather any history…

We began to pull some supplies out and open up the delivery room…

The next call came in about 3 or 4 minutes—-

Office: [anxiously] “BRING EVERYTHING OVER HERE….QUICK ! THERE’S NO TIME…. SHE’S GOING TO HAVE THE TWINS HERE !”  Hangs-up

We couldn’t all leave… One of the labor nurses grabbed a precip tray (small tray of emergency delivery items for a precipitous delivery) , put on a cover gown and ran down the steps to go over to the office. 

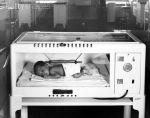
The two most experienced  nursery nurses grabbed two sterile newborn kits (these had sterile towels, washclothes, blankets, cotton balls, cord clamp, and a sterile shirt  etc..) and a few other supplies needed to care for the babies… opened the lid of the 2 Armstrong heaters and threw everything inside. —These old heavy metal heated units would open from the top and were on small little wheels. We usually used them to transport smaller babies from the delivery room to the nursery. They were already old back then and were not real easy to push.

Armstrong Incubator/Transporter

Armstrong Incubator/Transporter

This all happened very fast in a couple minutes. They were gone….headed down the elevator wearing their cover gowns pushing those old heated units filled with supplies. 

I stayed behind with a couple other nurses to watch our other patients. We watched from the window over looking the street.

Both nurses, running on short chubby legs were pushing those Armstrong Heaters down towards the street. (Think Danny DeVito and John Belushi in scrub dresses and nurses caps!).

One of the general surgeons had just come out of the hospital, saw what was happening and ran ahead of them right out into the middle of the busy street, held up both her hands to STOP all traffic. (Think Jane Fonda in a lab coat!)  If she had a whistle–she would have used it. From my window it seemed like the Keystone Cops. 

They got into the office, huffing and puffing. They told me there were a lot of people already in the tiny exam room. Dr.B had already delivered 0ne squalling baby girl probably about 4 lbs, about 4 or 5 weeks early.  She was pink with a lusty cry.  Dr. B was always so calm.. he was telling everyone to calm down while he tried to explain to the mother and the very faint shocked looking father that there was ANOTHER baby coming! Remember this was her first visit to our doctors? Turns out, this was her first prenatal visit ANYWHERE!!  You see….although Dr. B had told his nurses to call over to us a few minutes earlier with his findings, things happened so fast there in the office that he hadn’t QUITE really explained it yet to the parents. Twins were often a surprise in those days anyway, but this poor mom and dad had really just arrived in this country, let alone get in the door of the doctors office and promptly have TWINS!. 

Back to the delivery. The second baby was coming frank breech. No worries, we did that all the time. They told me Dr. B asked the labor nurse who had arrived first to open up one of the sterile packs and use one of the sterile towels to help hold the baby’s feet while he skillfully delivered the arms & then head of the second squalling 4 lb baby girl! The 2 nursery nurses wrapped up the babies in the sterile towels and wisked them both right out of there in the Armstrongs, out of the office, back to the street. (I doubt they let the mother have any time with the babies. That’s how it was then…… 😦 )  Like a well rehearsed skit, our lovely lady surgeon was waiting and once again— held up traffic so the nurses and babies crossed quickly and safely.  

I watched them coming back up the sidewalk and was waiting as they got off the elevator. They asked me to then help start the admission procedures in the isolation nursery. (They were born in that “dirty” office under unsterile conditions afterall!) At that time, babies delivered outside the “sterile” hospital were always watched in the Isolation Nursery. 

The mom came over by ambulance up to the delivery room to deliver her placenta (one placenta- they were indeed confirmed identical). The father was scrubbed up, gowned up and finally allowed to really see his little baby girls. I was the one to bring him over to the heaters. He was crying so hard. He was really in a state of shock and so emotional.007 I thought he was so shocked from the surprise of twins and the burst of frenzied excitement the birth had been……

This is when he told me that one year ago, in their country, his wife had suffered thru the birth of a stillborn baby girl ……… and now they had TWO healthy baby girls!!!  Can you imagine??

This family continued to grow as they stayed in town, both studying at the university. Her next baby was 10 LBs and born by C/S….. that’s another story.


Breastfeeding, Bottle Feeding and…. Somewhere In-between…. Why the Guilt?

There has been so much discussion circulating in the blogosphere right now about breastfeeding.  I thought I’d add my 2 cents because….I have an opinion and….. I have just a little experience in this field both in study (2 year Lactation course, IBCLC for 10 years, current CLC) and in practice (35 years).

I thought I knew so much in 1988 after nursing 3 babies and assisting others for nearly 15 years. I actually thought I could just take the IBLCE exam based on my experience!

I was so ignorant and naïve!

I started to talk to some IBCLC’s and my eyes were opened wide to the real world. Up to that point, at that time, (I sadly and guiltily admit) I had no idea about the volume of study and research in the field of lactation. I had NO idea just how wrong we were doing things at my hospital.

I launched into a lactation course, soaking up all I could, 3 years of study preparing for certification. I set out to change the world… at least my world. I wrote big proposals for the hospital. I applied for grants to fund a lactation program. I developed education competencies for the staff. I started breastfeeding classes. I thought everybody shared my passion, that they too would want to learn …. because I was right!!

Instead I was the target of all the boob jokes you could think of and I had almost no support. My ideas were rejected left and right.

Long story short…it took me a long time to come to terms with accepting small changes, taking baby steps…..continuing to do the best job I could with each mother-baby couple and to keep a positive outlook. I needed to remain realistic about how much I could actually accomplish one step at a time. Slowly I began to have people under my wing trying to learn. Yeah!

I learned a lot about how to approach physicians, co-workers, managers and most of all …. mothers.

I am not an expert in journalism or critical analysis so this is my opinion of what is going on right now. 

There have been some irresponsible journalists, those who have a bigger platform than most of us, writing negatively about something they have not studied or truly researched. They are expressing their opinion and including an emotional component which has, in my opinion, gotten the reaction they hoped for from breastfeeding advocates as well as those who concur with the authors. More hits, more readers. I feel they have twisted the facts to benefit or support a point they want to make. I read some of them.. other’s I really just scanned then brushed off so I don’t know everything that’s been said. On the positive side, these articles possibly give us a larger platform to provide correct information to a larger public in reply.

I read a lot of blogs and I really respect and admire all the research that many breastfeeding advocates put into their fabulous posts. These are educated women who are trying to provide current accurate information! (@phdinparenting, @bfmom, @MommyNews , @JakeAryehMarcus, @blacktating ,@AmberStrocel,  and so many more). I applaud their passion and breastfeeding advocacy. They are doing a very important job. Breastfeeding IS very important and deserves advocacy, protection and support! There are still large scores of women out there making choices with only tiny bits of information, who really do not know the important benefits of breastfeeding. It is because of this, and because we still haven’t met the US Dept HHS Healthy People Goals for 2010, that breastfeeding advocacy needs to continue. I have been there, advocating in a time where I faced great adversity and a lot of negativity. I am bothered that it still exists…and exists now in so many new ways.

I am more disturbed that some mother’s out there are upset. I always try to understand just WHY a mom feels guilty if she chooses to formula feed or do some combination of formula and breastfeeding. I always hope she’s made her choice with good information and that it is her own true choice. Then good for her! I am not to judge. She needs to be comfortable and confident with her decision. Perhaps her guilt comes from how one single little word or sentence was said, even if what was said is accurate and true. Perhaps her guilt is coming from her own internal struggles. I don’t know.  She needs to come to terms with that herself,  and not punish herself and or publicly criticize the advocates saying they are causing the guilt.  Although there are some very zealous advocates out there, I feel in my heart they are not trying to make any individual mother feel guilty. I read a comment from a mom somewhere that said something like… “perhaps if moms knew it wasn’t all or nothing, maybe more would try breastfeeding.”  My first thought was..why do they even think that..are there really mom’s who feel it has to be all or nothing? Is this causing the guilt because they don’t think they can breastfeed exclusively for the first 6 months as the experts recommend?? 


Over the years, I have learned this:

  • It is inappropriate for a health care professional to indicate to a mother directly or indirectly that formula feeding and breastfeeding are equal. Human breast milk is the superior food for human infants. Properly prepared infant formula is an acceptable substitute for those who cannot or choose not to breastfeed.
  • The first approach is probably the number one factor in gaining a mother’s interest in what you have to say.
  • The education process to a mother needs to be in small doses, sensitive to her unique learning abilities, her cultural beliefs and practices and most importantly, her choices and individual breastfeeding goals.
  • With that in mind, try to provide her with the information she needs to make her decision.
  • Never overestimate a mother’s desire to breastfeed her infant.
  • Never underestimate a mother’s desire to breastfeed her infant.
  • Listen to the mother; help her define her true desires and goals.
  • Many times, the first question she asks may not be what she really wants to ask.
  • The mother’s individual breastfeeding goals, how she defines them, how important they are to her and how she relates them to her actual breastfeeding experience all help define how she measures success.
  • Support the mother, support the mother, and support the mother.


Here are the top 3 responses to the feeding choice question pertaining to breastfeeding at my facility on admission:

  • “Breast and Bottle”
  • “I’m going to do both”
  • “I’m going to ‘try’ to breastfeed”

To each of these I respond very positively with something like… “Great! Tell me what you’ve learned about breastfeeding.”     I will then ask the mom a few questions to somehow find out her true wishes.  

Then I say  “We will support and honor however you wish to feed your baby.  I’d like to give you some information so you can really understand and then tell us what you’d like to do.”  

 I explain some things,  i.e.: how the milk production works, the importance of early feeds etc.. and how formula introduced at that time could  interfere with the process of production, the baby’s ability to latch properly and so on… I usually end with..”We usually recommend to  focus on breastfeeding for now and then offer bottles later after milk supply is established if that is how you’d still like to manage feeding”. ETC…ETC….  Here’s what I then see:

  • There have been so many mom’s who — after a little  bit of information decide they would like to focus on breastfeeding. There have been many who totally fell in love with it.
  • There have also been many who really didn’t want to breastfeed after one single feeding.
  • There are many many still that like to breastfeed and bottle feed in combination right from the start. If they have the right info and understand how things may progress… I still say “Good for you!”
  • I have seen many continue that way for months and they are very happy with that.
  • I’ve seen many mom’s “partially” ( I don’t like to say it that way) breastfeed and feel very proud. I say “good for you!”  They don’t think of it in terms of “exclusive” or “partial”… It’s more like any breast at all…. is breastfeeding vs. no breastfeeding at all.
  • There have been many who also never wanted to try until all of a sudden they see milk leaking!
  • I’ve worked with mom’s where I can see tremendous improvement in her situation, I think she’s going to keep going…but she decides to totally quit. I simply praise her for all her efforts and help her feel proud of herself.
  • I’ve worked with mom’s who have hardly put forth any effort to overcome small obstacles, I think they will probably quit outright… Then..I find out they are the ones exclusively breastfeeding down the road.

I got a comment from a breastfeeding mom @TheFeministBreeder that I absolutely have to share. She describes her own experience in the full comment and on her new blog post.  She comments:

 “Yes, I think that’s the most important part – informing a mother of any and ALL benefits/risks to supplementing, and helping them work through the option they choose.  But to tell a mother to supplement without explaining that it could undermine her efforts is just plain mean.  And too many medpros are doing it.  I’m glad there are more nurses like you who will give out the real information to empower a woman to make her own choice.  My smart friend always says ‘It’s not really a choice if you don’t have all the information.’ “

For those mom’s really trying to breastfeed and struggling, there’s more than I can say right here to cover that. I’m sorry for your struggles and hope it gets easier for you. It is important to have a skilled competent support person assisting you who listens thoughtfully and helps you get to the root of your problem… and helps you define and realize your goals. If you are experiencing guilt from your struggles or from not being able to fulfill your goals, desires to breastfeed….I think that kind of guilt is different from what I’m trying to discuss here. I am not a an expert on that. It is valuable to get the best help out there that you can as soon as possible.

I’m adding this after reading some comments on other blogs.. When approaching a mom to observe or assist with the latch process…. Permission is a must! I ALWAYS ask the mother if she would like any assistance with the latch or if  I may observe how well her baby is latching….. If that answer is yes… The next question is ALWAYS.. May I touch your breast? (if that needs to part of the process). I prefer to help moms by having the mom and BABY do the latch. I try to keep my hands out of it.  All nurses and LC’s should practice this. I am sorry for the mom’s who aren’t asked permission to be helped or touched.  😦


One of my favorite things I like to say to any breastfeeding mom is:

“Try not to make any final decision when it’s dark outside”.


On another note, regarding some reader comments on various blogs about public breastfeeding, a skimpy bikini or the bathing-suit issue of a favorite sports magazine show more skin in a provocative, sexy way than any mom breastfeeding. Even the movie stars in their gowns with plunging necklines are showing almost the entire breast! Somehow, that is OK. There are volumes of video footage and photos all over the place… even on billboards. It is sad that the public opinion of a baby breastfeeding (the most natural way for him to eat) is something that should be done in private … yet young girls are encouraged by media to bare more and more skin. Of course being discreet while feeding is important, but I can assure you, most girls in a tiny bikini are thinking more about “tacky exhibitionist behavior” than a mother breastfeeding her baby. Why aren’t law-makers focusing on any of that?

Wordless Wednesday…..

When Blood and Birth were considered CLEAN

When Blood and Birth were considered CLEAN

Thought I’d try this Wordless Wednesday style post. I give you a question….

Do any of you remember when Blood and Birth were considered CLEAN?

No gloves needed or used unless you would be STERILE or handling contaminated items??

Anyone??


No gloves

No gloves

Scary 1975 Breastfeeding Policy

 This story is about

VINTAGE Breastfeeding information

NOT Current Information


1979 Father wearing gown and mask to attend feeding

1979 Father wearing gown and mask to attend feeding


I have attempted to give an overview of our Maternity Ward as it was when I started to work there. I mentioned how “Once delivered, the baby went to the nursery and became the immediate property of the nurses, only to be seen from a window and allowed to be with the mother at token intervals. The poor little baby was often keep without food/ only water for the first 12 hrs. (Breastfeeding was something only the hippies did.)”

The thought process, as I was instucted even in nursing school, was that most newborns needed to rest after birth, and didn’t require food for 4 to 24 hours. They felt that postponing food would allow time for the mucous to be cleared from the throat and the baby would be allowed ample rest after the exertion of birth and all that handling by doctors and nurses as they provided the necessary care.  My nursing school textbook (Marlow, Pediatric Nursing, 4th ed. 1973) even goes so far as to say that this lag time would allow the mother sufficient rest before giving her infant the breast because….. this first offering is…… difficult. ( Oh… You’d better rest up, dear…)

Another thought process that unfortunately is still around today was that the nurse should not encourage the mother to breastfeed over bottle feed…. least she arouse or cause any maternal guilt feelings. My old textbooks all did list some basic benefits of breastfeeding and proclaimed this as the ideal food. Ie: easier to digest, natural diet for the newborn, convenience, availability AND the provision of identified and unidentified substances which may be protective.  The nurse should provide the information to the mother but not encourage her. They felt prepared formulas (Evaporated or whole milk formulas with added carbohydrates) OR the newer commercially prepared formulas were an “equal” substitute. We did have a full formula preparation room in the nursery with a refridgerator, range, sterilizing equipment etc. When I started, the Similac and Enfamil reps had already just hooked up the hospital with the marvelous free individual bottles of their products which were piled high on top of the former work area for formula prep. I don’t know when they actually stopped making it themselves.

Our 1975 Hospital Policy & Procedure  *

  • We start with NPO (nothing by mouth) for 12 hours.  Then feed one feeding of sterile water to confirm the infants ability to swallow.
  • If the baby has excessive mucus secretions, he should be fed 5% glucose water (G/W)  every 4 hours for the next 12 hrs before his first breast feeding.
  • The father may be present for feedings provided he is properly gowned, wearing hat and mask and has scrubbed hands.
  • For the first breast feeding,  teach the mother to cleanse her nipples with the cotton ball (soaked in a Benzalkonium chloride solotion) and teach proper latch-on techniques where-by the mother should cradle the baby near her breast, stroke his cheek so he turns and assist him to “grip” the nipple when he opens his mouth. Place the baby at both breasts for no longer than 2-3 min each side to avoid sore nipples. Feed the baby 5% G/W if he is still hungry when removed from the nipple.
  • Feedings should be every 4  hours, the mother should cleanse her nipples as above before each feeding.
  • If the baby should cry within 3 hrs of his last feed, he may be offered more 5% G/W.
  • The time spent at breasts should gradually increase to 3-5 min each feed for the first 2 days then continue to increase up to 10 min each side by the 4th day. When her milk begins to flow and the baby will actually be receiving milk.
  • Instruct the mother to pay close attention to which side she began and ended each feeding so she can alternate which side to begin the next feed.
  • Babies will usually require 6 feedings a day for the first several weeks.
  • Once lactation is established, she should be instructed to limit a feeding to 20 – 30 minutes total per feeding. The baby gets 90% of his milk in the first 5 minutes, any additional time is for his enjoyment. Some babies may “cling” to the breast after feeding and may need to be removed. Teach the mother to use her finger gently in the babies mouth to break the suction and remove him.
  • Babies may be taken to the mother for a breast feeding “on-demand” if so written on the chart by the physician


(*This is a combination of information I have from a scanty old policy,
what I remember
and interviewing some older former colleages about what we all actually did.)

If we were unable to get a baby to latch on, we had one tool available to us at the time. We had a hard rubber nipple on a glass base shield that we placed over the breast/nipple and we used the same timing of feeds.  We would only help a mother pump her breasts if she was engorged. The only tool we had to assist her with this was a bicycle horn hand pump. 

There were some pediatricians who were starting to be flexible and improve the approach to breastfeeding in a more natural sense, encouraging initiation earlier and more frequent feeds “on-demand”. There were more professionals opposed to that train of thought and continued their same practices.  When the women started coming in and requesting a better approach to feeding…. they were sabotaged by the nurses who then fed their infants “white water” while in the nursery so these babies would sleep until the next designated feeding time. 

This was 34-35 years ago and I still work with nurses today who have some of these thought processes behind what they do. Many of the older physicians, if taught anything in Med school, were taught similar management protocols. It is such a difficult retraining, re-educating process that some of us face. 

Just last week.. a brand new RN/BSN asked me how the newborn was supposed to survive on colostrum alone?

She was blank faced dead serious. 
I started my answer with…”You are not the first nurse to ask me that very same question and it’s a good question. Here’s why etc……..”
I hope I answered her well enough so she can someday teach the next one and the next…..
We really need much better Lactation Education 
for our Doctors and Nurses.
They should not be so uneducated or ill-equiped 
to properly care for and advise the mother’s in their care!

Our HOSPITAL’S First Planned VBAC

I say our hospital’s first planned VBAC (Vaginal Birth After Cesarean)….. however a prelude is necessary because the actual first VBAC I can remember…. totally freaked everyone out. Here are the stories:

Sometime in the mid 70’s -circa 1976, a mom came in to L/D for a labor check. She was near term with some regular contractions, a little bit of bloody show. The nurse calmly wrote her name down in the notebook…. [Yes– a notebook, that’s the only way we kept track of labor checks back in those days. No medical record, no registration, just a name in a book and the day they were here and checked]… She was getting ready to gather more information when the mom said she had a history of a prior C/S.
Suddenly all the nurses were scrambling—“Quick, call the doctor!” “Quick, shave her belly,” “Get the Fetal Hearts” “Call the OR and tell them we have a STAT C/S”…We were all busy quickly getting her ready for the OR.
This little baby, however, definitely had other ideas. The mom told them she had to go to the bathroom…
Someone said: “Not now honey, we’re going to get you to the operating room to have your baby.”
The Mom: “But—I have to go….. AUGHHHH” (loudly grunting)
One of the seasoned nurses threw the sheets back and low and behold, that little baby was crowning!! “Doctor W– No time for the OR– This baby is coming!”
She did deliver vaginally, quickly, and everyone was in a state of shock!
I was thinking– I didn’t think that was possible–they told me once a cesarean always a cesarean—they told me the uterus would rupture–that the mother would hemorrhage. She and her baby were just fine. I realized once again that I had a lot to learn!

Fast forward now to 1984.

I was sent a nicely written post on the VBAC Pendulum by Dr Shelley Binkley which discusses the rise and fall of VBAC’s in the US and makes for very interesting reading. There’s been tremendous controversy surrounding this topic.

VBAC’s were widely discussed in the literature at early to mid 80’s and many women were interested…the doctors???– not quite so sold on the idea.  However, in the late 70’s early 80’s, we had one very progressive young doctor (Dr.B)  in the main OB practice.  He was responsible for many of the advances we had in a more natural approach to childbirth.  He was willing and eager to give this a try. 

I am not sure what he may have discussed in the office with his patients or how he may have selected his first patient who could try for a VBAC.  Knowing him, he may have brought it up to mom’s instead of the mom bringing it up to him. Anyway– sometime in the summer of 1984 we heard we would be having our first VBAC! She was due in December with her second child. Her first baby had been delivered at our hospital by Dr. B via C/S because of some fetal distress.  He knew her history and had full access to her records to know exactly what type or uterine incision she had.  She was young, healthy and continued her pregnancy to term without any complications. She was very excited. 

The hospital staff was a nervous wreck.

Where oh where were we going to labor her so that should ANY complication arise, we could do the fastest C/S possible??? We didn’t do C/S’s on our unit. The OR was down a floor and in another wing!!! Such a dilemma.  They finally decided to use the tiny windowless isolation room of the Recovery Room right outside the OR.  They decided to bring all the equipment from L/D down to that room to see how it all fit. We had a regular bed,overbed table, the fetal monitor, some other IV equipment/meds/ supplies etc.. a chair for dad, stool and sm desk for nurse…all crammed in the room. (OK- we scrapped the desk..that was rediculous) We were literally practicing like when they do separation surgery for conjoined twins!!  Quite the production. 

Ready or not, here she comes…….arriving in labor almost a week late at 40 5/7 weeks.  She was in very early labor much to the relief of everyone involved. OF COURSE I was on duty! OF COURSE I was elected to be her nurse! I was after all, the most prepared (say all my co-workers).  So while other’s got the room ready downstairs, I admitted her. There were no special consents at the time.  My orders were continuous fetal monitoring,  start an IV right away, AND insert a Foley catheter so we would keep the bladder drained, avoid any excess pressure on the uterine scar and keep her from needing to get up.  I also had to do a big shave prep in case of an emergent C/S. We took her down to that tiny closet of a room when it was ready, around noon. She was still in early labor.  The plan was to do a double set-up in the OR for delivery. That meant a whole set-up for a vaginal birth and a whole set-up open for a C/S complete with the entire OR team. They would call them in when she was in active labor. She had progressed to 7 or 8 cm with her first baby before needing a section so the thought was she’d go fast this time. 

Early labor continued into the late afternoon. All the managers involved kept stopping in repeatedly with all the same questions:….. “Is everything alright??”….. “Any problems??” …..”Any sharp pain in the lower abdomen?”….. “Any blood in the urine?”…….. “How about any excess vaginal bleeding?” ……..They were making me crazy.  We didn’t do any Pitocin augmentation. This poor mom was just in bed the whole time, in the closet with the single bright light, moving around when I suggested changing positions. Finally she headed into active labor and then did progress quickly to transition.  The membranes ruptured spontaneosly and the fluid was clear. The baby was great on the monitor!  The mom was a trooper, never complained, always smiling in between contractions, agreeable to whatever we said.  They asked me to stay and I stayed…. long past my shift.  

They called in the OR teams. I wasn’t nervous anymore. Get me alone with my patient– away from the nervous Nellies and we can connect and work together through labor. It helped that I had seen that unplanned VBAC so many years before and that I had tremendous trust in and respect for Dr. B.. He was there past his shift also. I had already helped her through so many contractions. She didn’t have the slightest symptom of problems. I had her pretty relaxed, she went thru transition and headed into the second stage in good shape.  At this point, they wanted to move her to the OR for pushing. I think back and feel so bad for her… She was however, still excited and still very agreeable.  She pushed on the hard delivery table in the OR in front of the assembled teams. Talk about performance anxiety.  She sure had a lot of coaches!!

She delivered and 8lb 14oz boy named Michael later that evening!!! He was 20 1/2 inches long, his apgars were 8 and 8, just needing some blow-by oxygen in the OR.

There were no complications. This mom came back and had a few more VBAC’s ending up with 5 children overall. I don’t remeber how many VBAC’s we labored in that rediculous closet of a room before we would keep them in L&D. 

I admire this mom for her strength and courage. I thank her for all she taught me…taught us..

Michael will be 25 years old this December!

If you like this story or have any interest in how any specific childbirth element was first seen or has evolved, Please comment or contact me! Thanks

Medical Science vs Natural Childbirth 

I sat here to write the story of our first planned VBAC and realized as I scanned my other posts that I had to tell just a little more history to help explain the attitudes of the times.

During the mid 70’s early 80’s… our country was changing in many ways. In the medical world, Obstetrical medicine was becoming more specialized with the development of many subspecialties including  “Perinatology” and “Neonatology”.  Perinatology by definition is the study of the unborn fetus and recently born infant during the first several weeks of life. It was the changing concern of obstetricians from a sole focus on the mother’s health to one which is balanced between the mother’s health and the unborn or newborn. ACOG started to offer a specialty certification exam for perinatology  in 1974, and in 1977, the Society of Perinatal Obstetricians (now called the Society for Maternal-Fetal Medicine) was formed.  The term used to describe a Perinatologist today is a Maternal-Fetal Medicine Specialist.  This specialty is the management of high-risk pregnancies and the assessment and treatment of the fetus. Neonatology (established 1975 by the AAP) is the study of a highly specialized care of the newly born infant especially the ill or premature newborn infant usually hospital based in NICU’s.

Young women were becoming more and more interested in a natural approach to childbirth. People all over the country were driving maternity services to offer the availability of birth options for these moms. The ICEA [International Childbirth Education Association] came to our town in the late 70’s and a local chapter was born. “Freedom of choice based on knowledge of alternatives” in childbirth was a motto on their pamphlet information. There were some individuals in the community going for the new certification of childbirth educators. They were educating some new mom’s about birth options…… that we, the staff hadn’t learned about let alone developed as an option for our patients. Many on the staff scorned this movement. It seemed to me that these changes were all happening at the same time. We were learning about advances in observing and monitoring the well-being of both the laboring mother and her unborn fetus, preventing complications etc…. arising from the research studies done from the emerging sub-specialties. We had one fetal monitor and purchased another. As soon as the specialists found that continuous fetal monitoring was advantageous to picking up potential problems in advance, to possibly avoid or prepare for complications, there was a natural childbirth revolt against the constant recumbent positioning that EFM (electronic fetal monitoring) seemed to require. There were more examples as with IV fluids or access and other routine procedures. The nurses didn’t understand. They were just trying to do what science and our doctors were telling them…[though not always willingly as some were afraid of the newer technology.] To them, this group pushing a natural childbirth movement was the same population that had just wanted to be given drugs, put to sleep and “wake me when it’s over” crowd.  

I realize that although these advances in science and the movement of young people seeking natural childbirth options seemed to happen so close to the same time in my world, it probably didn’t happen this way for all of the country. Here, I really think it probably greatly contributed to the attitudes of nurses and doctors I worked with at the time. Those professionals who just couldn’t relinquish control. They were learning more about the science of birth, of monitoring and couldn’t quite allow or see how the “natural” component could fit in. Those individuals often were guilty of the abuse of professional power, the use of misinformation and the blindness and arrogance to maintain control of the birth process… taking it away from the mother.  Those professionals who should have known better.  They did not know of the rights of childbearing Women, or of general patient rights for that matter. Unfortunately– there are some who still have these control issues.

That’s another story….

Stand and Deliver? There’s No Stopping Her

I recently read a post from another blog about the study cited in The Cochrane Library discussing patient mobility & upright positions in early labor. The summary talks of the authors’ conclusions that there’s evidence supporting walking and or upright positions in early labor which can reduce the total length of labor without being associated with any increase in medical interventions or untoward affects on mom or baby.

Thus I was immediately taken back to 1977, long before any such studies. This woman certainly didn’t read them! She wasn’t my patient…. my patient was in the bed next to her.  (No single labor rooms back in 1977.)

When she arrived on the unit, she was already entering active labor. Her contractions where about 2-4 mins apart lasting a good 60 seconds and she was WILDLY out of control. This was her first baby, and at 4 to 5 cm dilated, she was thrashing all over the bed refusing any measures of support, IV or pain medicine offered to her by her nurse. She was probably offered “Twilight Sleep” consisting of Scopolamine and some narcotic–which we used a lot and many mom’s had hallucination or delirious type side effects.

It is important to note here that this woman was 5 ft 11.5 in tall and probably weighed a good 225lbs.  I remember this because she seemed huge and I thought she was at least 6 feet tall and looked at her chart. Her nurse was only 4 ft 11.5. The doctor on duty that evening was of Asian decent, very petite and about 5 ft, 1 or 2 in.

Back to the poor mom in labor. I couldn’t help much because I was assisting my own patient and a few labor checks that were hanging around. No other labor coach or father of the baby around in those days… It wasn’t long before this run-away train of labor progressed to point where mom was fully dilated and had the urge to push. Many women of this body stature have quick, sometimes fierce labors…..I have no study, just my observation.
Here’s what happened:
Mom: “I have to get up out this bed”
Nurse: “We have to start pushing now, I need you to take some deep breaths and when that next contraction starts, you can push with it.”
Mom: “Mmmh Hymmm I have to get up out this bed!!! Do you hear me???”
Nurse: “I hear you, we can’t let you get up right now, the baby will be coming soon… Let’s try to focus on pushing”
Mom: “I AM TELLING YOU….. I HAVE TO GET UP OUT THIS BED!!!! YOU NEED TO HELP ME!”
Nurse: “I am trying to help you”
Mom: “I’m gettin up”
Nurse: “Please try to relax”…blah blah blah

There was no stopping her. This woman stood up, ON THE BED, placed her hands on the ceiling, spread her legs and began to push—loudly !
There wasn’t anything to do except accommodate her. The nurse grabbed the “precip-tray” we use for emergency deliveries and called the doctor in. They put the large metal side rail down and these two tiny birth attendants were actually the perfect size to get in under her large frame and assist the delivery of the baby. It was an awesome sight!
I wonder if she ever reads about the research now and thinks back at how she was ahead of her time..she knew what her body needed to give birth.