Skip to content

Wordless Wednesday… 1950’s “Good Wife Guide” and more…

goodwif1A guide for a “Good Wife” and more…….  vintage 1950’s and 1960’s American culture Photos found on this amazing collection of photos. Great find!!! I really remember many of these things.. Born in 50’s, preteen to teen in 60’s to 70’s.

Fun Memories

Click here for all the photos!

http://www.billsretroworld.com/RETROLIFE.HTM

I recently found this first link wasn’t working now…so I found another copy of this guide here:

http://www.snopes.com/language/document/goodwife.asp

http://www.snopes.com/language/document/goodwife.asp

Little Old Men… & Nursing in Public

Welcome Readers…to my first Carnival of Breastfeeding post!
This month’s topic is “Nursing in Public”.
Links to all the Carnival Posts are listed @ the bottom. I’ll update this as more are posted.

Keep checking back and Enjoy!!

My first baby was born in sunny Florida during a particularly hot stretch in May 1979.  Although I was an OB nurse, I knew very little about breastfeeding other than what my older co-workers had taught me—which was not all that correct or very helpful information. Luckily, I had a great friend who was nursing her 3 month old at the time my son was born. She really showed me the ropes. It just so happened that she was the one who took me home from the hospital. We had to stop at the store for a few items so we went in to a “Publix” supermarket with both babies in our arms.  My newborn son began fussing to nurse soon after we hit the air conditioning.

I said.. “I’m going to have to go back out to the car and nurse him.”

My friend says “Oh..You’ll do no such thing.. You’ll die in that heat.. Just hook him up and keep shopping so we can get finished and out of here!”

Me- “Nurse him in here?”

Friend- “Well if he’s hungry.. yeah!.. (after looking at my face) Oh stop worrying about it..go over to a deserted aisle, get him hooked on and put your receiving blanket up near his face… nobody will know!”

Me- timidly…above the louder howls.. “Alright, be right back..”

I found the most private place I could. I started cursing that complicated “wonderful nursing bra” I just had to have. (Remember..this is 30 years ago… this bra is now an antique!) My skills handling newborns allowed me some grace as I attempted to multitask by stooping down, prop my loudly crying baby on my partial lap, use 2 hands to fiddle with the damn nursing bra, then get him back up near my finally free boob and latched on.

Ahhhh~ quiet, happy, drinking baby!

Still stooped down, I peered slowly behind me — expecting that a large crowd must have assembled. Somewhat surprisingly, everybody was just going about their business and I happily realized that noone was looking at me! I stood up, made sure I wasn’t showing anything, and walked off with my happily nursing baby to find my friend.

It’s amazing how many people want to see a quiet baby as opposed to a screaming infant!

A sweet little old man stopped me first and asked me how old my baby was….”3 days”, I replied. He peeked in for a closer look and he actually didn’t get it right away.. “I can’t really see his face.”.. I said “Well- he’s feeding right now.”.. He just said..”OOPS….sorry about that! Well he’s a cute one!” then walked off.

The next person who stopped me was again.. a sweet little old man. He was very smiley and jolly. He asked all about the baby but didn’t lean over to look like the other man. I quickly said he’s nursing now and then answered all the small talk.  He never seemed uncomfortable about it at all! That probably gave me a lot more confidence. We parted ways and I finally found my friend. She gave me an approving thumbs up, asked me to hold a basket with my other hand and said we were almost done.

Another little old man stopped us by the register to ask about both babies. We gave him all the small talk answers and let him know my son was nursing. This guy was a real sweetie, commenting on how lucky kids were that moms were starting to “nurse their young” again and ‘good for you.”  He never tried to look in at my son. He didn’t seem embarrassed by the process at all. He was the coolest guy!

I left the Publix Supermarket on my way home to begin my life as a mommy…. with a little public education bonus.  Encountering those sweet little old men while feeding my baby and receiving their positive type feedback was the gentle support I needed. I went on to feel empowered to nurse in public for all three of my babies…  Those little old men were just so supportive! ~ When my baby was hungry, he needed to feed and it really didn’t matter where I was at the time.  Thank goodness for my friend’s wisdom and support to go for it!

I became a lactation professional while nursing my last baby. It was then, only after I really became more aware of issues surrounding nursing in public that I actually took any kind of public action to empower other moms.  I’ve done lots of different little things as the years have gone by. I want to mention one fun way that I thought I could help gently re-educate some of the “new” sweet little old men of this day and age.  Our local paper has a lot of little retired guys commenting back and forth on various local articles. I’m guessing their age and status by all the things they say. I took this opportunity to possibly educate some of these forum readers about breastfeeding rights in public.  Every once in a while, on the forum, I put out a little snippet on nursing in public… and sit back and watch what they have to say in reply! It’s quite fun!

Here’s an example I wrote on a long forum discussion a couple years ago on a breastfeeding article:

On another note, regarding a reader reaction in the forum, a skimpy bikini or the bathing-suit issue of a favorite sports magazine show more skin in a provocative, sexy way than any mom breast-feeding. Even the movie stars in their gowns with plunging necklines are showing almost the entire breast! Somehow, that is OK. It is sad that the public opinion of a baby breast-feeding (the most natural way for him to eat) is something that should be done in private … yet young girls are encouraged by media to bare more and more skin. Of course being discreet while feeding is important, but I can assure you, most girls in a tiny bikini are thinking more about “tacky exhibitionist behavior” than a mother breast-feeding her baby. August 1-7 is always World Breast Feeding Week. The theme this year is “Welcome Baby Softly,” focusing on the importance of the first hour or two after birth. Learn more about it. I would love to see the paper do an article on that.

This one provoked a few responses in both directions and sometimes there were a few people who actually thought out loud that …gosh maybe I was right… never thought about it that way…etc..

Here’s an example I wrote on a recent article about the appropriate % amount for tipping :

I have never left an establishment without tipping– however, I also tip according to service up to 20%. If there are unkind reactions to small children in a FAMILY establishment, they will be getting a bare minimal tip for sure!! I do my best to keep my children behaved with table manners AND respect other patrons… but fact remains, they are children! I cannot possibly be prepared for every behavior or an accidental spill. In addition, my breastfeeding baby may be hungry.. By PA law, I have the right to nurse my baby in a public place wherever he and I are allowed to be. I am discreet.. I am protected by law… I don’t need an unkind comment from servers. They do not get a 15-20% tip if nasty, unkind or disrespectful comments have been made about my children or my breastfeeding baby!

This provoked a foray of comments ranging from ‘good for you’ to ‘you should be in the back booth…controlling kids etc..’  Sometimes the opportunities to educate others come at unexpected times but produce amazing results!

On a few occasions, other readers were supporting my comments and

helping to educate those sweet little old guys with me!

😉

Carnival of Breastfeeding Post Links (Check back for updates)

I’m Proud of my Hospital….~ this week ~

~I’ve reason to be a little proud of the care given this week.008

I hope this is a continuing trend of attention to detail, utilizing evidence-based practices and compassion, listening to our patients and providing them with options and the best possible care…. I’ll give you a few details about each as you read on… In summary, this week we have had the following situations:

  • A 25 week-er walk-in with a precipitous delivery stabilized & tranported quickly
  • Twins! Vertex/vertex –turned breech– turned vertex~ delivered vaginally
  • A Heroin/Cocaine  addict identified, baby able to be treated appropriately so comfortable transition
  • Safe Haven newborn about 1 day old.. placed up for adoption
  •  Homebirth Transfer handled with great respect overall and most importantly, the mother is happy with her experience.

Whew! We have a lot of busy weeks but they don’t always have this intensity or variety! I feel proud because there may have been a few things done differently due to recent conversations I’ve had…Plugs I’ve made… and I keeping putting in little plugs to try to gently increase awareness & educate. I am an Instructor in Neonatal Resuscitation and Lactation.. sometimes the troops listen when I talk about other topics…. I’m no expert but I try to be current, correct and compassionate in care. (My 4 c’s)

Okay… the details for the first 3… stay tuned for the others…..

~25 Week gestation walk-in~

She came in with mild cramps and pressure. She didn’t report any fluid leakage but did C/O pink vaginal mucus. We had her in an exam room pronto. She had a gentle speculum exam which revealed hour glassing membranes thru an approximate 4-5 cm cervix..visually.  Hour-glassing means that the intact amniotic sac has protruded thru the partially dilated cervix and expanded like a bubble  in the vagina. She went right into trendelenburg. The transfer teams were called. It was soon clear she would deliver here and the baby would need to be stabilized and transferred. The NICU team contacted us back they would be flying up to retrieve. The nurses caring for her were tremendously supportive.  All procedures explained, options offered and decisions honored.  They got her records faxed over from her OB’s office so we had a little history.

Like a well oiled machine (from all of our drills), all the emergency equipment was readied, pediatrician in attendance, roles clarified. Once he was born almost without warning, precipitously, all at once, about 30 minutes later. He was quickly assessed, wrapped in plastic, ventilated, then intubated. We had a peripheral IV in place in case he needed meds or fluid volume. He had a chest xray and a blood culture/blood count sent.  He was kept warm, ventilated and appropriately oxygenated and had stable glucoses. He weighed in at about 700 gms (about 1 1/2 lbs). The team arrived when he was about 30 minutes old. They checked all labs, xrays and his IV line. They gave him Surfactant and pretty quickly and carefully,  loaded him in the transport incubator then got him out to his mommy for a visit before he was transferred. They answered all her questions before they left and we helped her deal with it all. The doctors discharged her shortly after that so she could get down to her baby.  At last report, he was doing just as expected for 25 wks, no other complications often seen at that gestation, for ELBW (Extremely Low BirthWeight) had come up. He was actually improving each day! So happy for everyone!

~Twins!~

She came in to the hospital already in very active labor at 37.5 weeks gestation. Her twins were both head down (vertex/vertex). She labored quickly, uneventfully and delivered Twin A at about 1 pm. With the ultrasound machine in the room, they scanned over her still pregnant belly to see where Twin B was and if he was still in position. Turns out that once Twin A had vacated the womb, baby B had a lot of room and he had moved into a transverse/breech position. That means he was more bottom first than head first anymore. Most Ob’s now don’t attempt a breech delivery even with the second twin.  They are quick to do a C/S…. This day, however, …. the Ob in charge called over an associate to ask his opinion. They brought the mom into the OR and prepared to do a C/S  if they were unable to get the baby in proper position. The point is they were at least going to TRY!  With the U/S scanner and 2 assistants, they did an external version and worked Twin B  back into a head down vertex position without complication. He delivered vaginally about 1 hour and 45 minutes after his brother! The staff kept the first twin in the room the whole time so they could all be together. I spoke to the Ob later and congratulated him on a great job.. he said to me that he remembered what we had talked about awhile ago (when I had written the post about a C/S for the 2nd twin), and had researched it himself. I was happy that any little plug I had made had sparked interest in researching the topic and possibly even influencing a decision towards better care! I am happy to report that both babies went home with mommy on day 2!

~A Heroin/Cocaine addict~
We are attempting to put together some consistant protocols for drug screening so that we don’t miss the opportunities to protect a newborn in need…. Some may not understand how important it is to sometimes screen the healthy and innocent to weed out those with problems…. They don’t always present in an obvious way. From my perspective, those individuals who are hiding something are very difficult to identify from outward appearance only. We identified a heroin/cocaine addict recently who was a very beautiful, well groomed, well nourished, affluent (seemed wealthy) woman who stated she was just visiting in our area, and had no prenatal care info or records with her…. she was in rip-roaring very active labor at 36 1/2 weeks with heavy vaginal bleeding and fetal distress. We thought we were headed to the OR but the baby had other ideas. We had little time to get more information before the baby was born. There was a small abruption but luckily, the baby was vigorous and did not seem to have suffered blood loss. The admitting nurse had collected a urine sample with a catheter insertion and sent it for drug screen. It came back positive for Opiates, Cocaine and THC. The baby’s urine also tested postive for Opiates, Cocaine and THC. Because we knew, we were able to start the NAS (Neonatal Abstinence Scoring) for signs of drug withdrawal and identify the signs quickly. If the baby is unable to be comforted by swaddling or holding or if we had 3 scores of 8 or higher, there are protocols set up for medicating the baby. The baby did require medication within 24 hrs. Once medicated, she was such a happy sweet little girl. The nurses named her “Molly” and we all loved her. She stayed with us all week until the pediatrician released her andChildren’s Services placed her in a foster home experienced with this kind of care. Unfortunately, some of the big drug problems have hit my area. Our local paper just did a big series of stories on local Heroin addiction problems. Apparently it is cheap and accessible.

I am going to publish this part tonite and tell the other two stories soon…

No Prenatal Care? …..What are YOU Hiding??

No Prenatal Care is usually a symptom of something--hiding some type of underlying problem. Sometimes it's very ugly. The most common encounters we have involve illicit drug use during pregnancy. We need to develop a comprehensive Maternal and Neonatal Drug Screening protocol to protect the newborn.

Read more

Preserved Children

I received this recipe from a friend quite a while back. I felt this would be a great place to share!

Ingredients:

  • 1 large field
  • 2 or 3 small dogs
  • 2 handfuls of dandelion blossoms
  • 4 – 6 clusters of daisies or other flowers
  • 1 brook or stream
  • smooth pebbles
  • 1/2 dozen children (more or less)
  • Basket of delicious foods

Recipe Directions:

Sprinkle large field with daisies and dandelions. Pour brook gently over pebbles then watch and listen for babbling.  Mix children with dogs, add to field and allow to run.  Cover all with deep blue sky and bake in sun. Nibble on contents of basket at any time while watching. When well browned……… cool in brook or stream. Alternate cooling could be in bathtub later that day if desired.

Follow this recipe frequently for sweet dreams and happy children!

Creek

Have one to share with me? Please leave in a comment!

OB Docs and Nurses Scoff at Homebirth

My community hospital’s views have never been in favor of any type of home-birth… whether it’s with a skilled professional  practitioner or a skilled lay midwife. There could have been some free unassisted births going on but we were not aware….  As I grew-up in this profession, I learned first from my experienced counterparts…then I began to educate myself and learned a lot from mothers and babies.  The doctors and nurses I worked with were all stagnant in their knowledge in my early years. They were satisfied with how things were.  I was young, I had an open-minded philosophy and an eager quest for knowledge.

In the later 70’s, just when we began to have mothers speak out and request a more natural childbirth, I had a few friends who enlisted the aid of some lay midwife in the region and arranged for homebirths. They all had a really nice birth experience without a single complication. Perhaps that was why I was open to the idea even though I was not personally involved. Besides some of the truly prepared couples who came in and had incredibly beautiful births….. that had been my first exposure as an alternative option to the knock’em out–pull’em out births I had been working with on the job. I knew my friends were very low-risk and had done their homework. 

   However, the hospital’s exposure to a homebirth in those days was only if the homebirth went awry for some reason or another and they came in our doors seeking help…  here’s what the docs and nurses would say to one another :

  • “Can you believe she planned to deliver at home???”
  • “How could she take take a chance like that with her baby?”
  • “The reason people started coming to hospitals to give birth was because mothers and babies were dieing at home….she must be crazy or totally insane!!”

   We’ve had planned homebirths come in for various reasons, as I am sure other facilities did…. (keep in mind that in my area, the usual birth attendant was a lay midwife). The situations bringing the mother to the hospital were often scary and upsetting for her. The most common were:

  • Fetal heart rate decels with or without meconium stained fluid 
  • Lack of progress with pushing mostly after many hours..
  • Higher than normal bloody show or bleeding–possibly abrupting
  • Breech, brow or face presentation
  • Retained placenta

Often the OB’s didn’t handle themselves well.. certainly not professionally. We had this one OB who would call for the OR to be opened before he even examined the patient or evaluated the situation…..regardless of why they came in.  And he often actually yelled at the mother, in the middle of her scary situation.

“Your baby will die if we don’t do an emergency C/S right now, why did you let this happen!”

Most often the backlash was directed at the midwife who cowered in the hallway- uninvited by the staff, left alone detached from her patient. She never left the unit though until she was afforded the opportunity to visit and speak to her patient. 

The two significant situations I remember which would fall in to statistical data for morbidity were:

  1.  An abruption which resulted in a crash C/S upon admission and a neonatal resuscitation with good response….(final apgars 3@one min then 7@ five min) positive overall outcome, no long term sequelae.
  2. A birth where the father (a chiropractor) was the birth attendant for his wife, a multip, encountered a shoulder dystocia and the baby ended up with a displaced fractured left humerus. That baby was in a crib with traction to realign the bone. The child went on to be an honor student at a local university after homeschool.

I feel that instead of the midwife or mother receiving hostility (or even the mother being wisked away to the OR without a trial of something if the baby was deemed stable..)~ the staff should have behaved in a compassionate professional manner, acting on any urgent situation with consideration that this mother is now experiencing not only labor but fear and grief over the loss of her beautiful planned birth.

Despite all the negativity from the staff, we never had a seriously bad outcome from attempted homebirths arriving on our doorstep.  We still have attitude problems, probably always will~ just as we do with breastfeeding.  I wish they could  look at it from my perspective. Those who choose homebirth today have better information to hopefully make an educated informed decision about their birth options and choose wisely. I really like Ricki Lake’s “The Business of being Born” among other’s. I hope those choosing homebirth are truly investigating all these options, deciding what is best for them and not making any decisions out of “anger at the system” or any sort of revolutionary zeal.  

  There is so much out there for medical professionals to be aware of other than what goes on in their tiny little realm, their little part of the world. My co-workers and doctors need to be better informed.  

Any one bad outcome (which most certainly happens in the hospital)  does not mean that every homebirth is a bad idea.

Wednesday’s Watch~ Children and Birth

Do American Children know this much about birth?

dematronas  …. de matronas… 

This YouTube video is a very well done example of the beauty of birth and the beautiful innocence of children.

These children are interviewed about birth and midwifes and babies.
They are very very smart indeed!
I found this courtesy of my new twitter friend @ketchup74.

From Spain or Argentina? with English subtitles.


Has anyone seen or found a video as beautiful or remarkable as this? Please send me a link if you have!

Check the comment for some great links already! Thank you!

In Memory of Daddy

Captain Thomas Joseph Shanley

Captain Thomas Joseph Shanley

Happy Memorial Day for Daddy
This is a day to remember those who risked their lives in service to our country. Today, I have been reading all the tiny bits of information written by his crew members, memories they put together as they grew older. My father was a pilot in the US Army Air Corp during WWII.  He flew as co-pilot of a B-17  with a crew in the 8th Air Force, 94th Bomb Group, 332nd Squadron.  They were based at Rougham, Bury St. Edmonds, England.
He did not speak to any of us of his missions or the  war when we were growing up. We asked, he always said it was secret.  He kept a lot of it hidden away. He probably had some degree of post traumatic stress disorder. I don’t think he ever really recovered. He was a wonderful man and taught me many things growing up. He died at a young age, 58 in 1982. What we know about his life during the war, we learned from these other crew members. I am very grateful to have a better understanding of what he went through, a better understanding of the hell of war.
I love you daddy.
I dedicate this day to you and to all the men and women like you.
Thank you

Cesarean Delivery of the Second Twin… Why? 

029I was talking to one of my on-line Twitter friends @onefinebreeder about twin delivery. I was telling her about how things used to be.. how vertex-nonvertex twin gestation’s were always delivered vaginally ….. and she commented on how it was sad that some of the old OB skills have been totally lost to surgery… So Very True!

I got to thinking about the first combination Twin delivery I had witnessed back in the very early 80’s. This was actually one of our own (hospital employee) nurses .  She was a multip…. around 37-38 weeks and healthy…no complications during pregnancy. Twin A delivered spontaneously, vaginally with a generous episiotomy as they often performed at that time… The baby , a girl, was about 6 pounds, vigorous and had no problems. We were all marveling at the first baby, checked fetal hearts on the second twin and started waiting for him to get in position.  Still before consistent ultrasound, we were not worried. However, we had a newer doctor who was attending this birth. He began to get concerned after 5- 10 min when contractions slowed and he was worried that if this baby was breech, he would have difficulty with the “after-coming” head. Up to this point, all I had learned was this can be a real concern if the smaller feet or buttocks present through a cervix which is not fully dilated. Much research was done later on but at the time, I did not know about it. He began to ask us to call the OR for a C/S. This was unheard of in my limited experience at the time…. my 70’s world. I thought.. how can they do a C/S now when one baby was already born??? I tried to be an advocate… (my early days… )”We have Piper forceps…”  I said meekly… “Have you tried to grab a large part and help bring the baby down… ?” This was my limited knowledge… all I knew to suggest. I kept wishing one of the other doctors was on duty that day.. or maybe we could call them???

In front of the mother, he said to me “I’m not going to have a bad outcome here!” By now it was 20 minutes or so. There was no cord prolapse, no drop in fetal hearts, no evidence of immediate trouble… the baby was seeming to work itself into breech position…. To the mother he said “Your baby is in serious danger and the best thing to save him is to take you for a Cesarean now!” “I’ll sew your episiotomy together while we are in the OR.”

I was in shock. She signed, scared to death of course. So we prepped her for the OR. She went up for a C/S of her second twin and repair of her generous episiotomy. Her second baby was delivered frank breech…  a beautiful boy about the same size and was also vigorous and healthy. I remember I felt as though she was almost assaulted. I remember feeling that this was a true rare event if it every happened before. There was no immediate access to information like today.

Luckily mom and babies did fairly well in the postpartum period even though healing from both the episiotomy and the C/S was difficult for her.
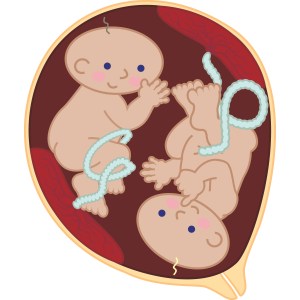
"How can I get out if I'm not head 1st ??"

" Psst-- How can I get out if I'm not head 1st ??"

I wanted to see how much research I could find on this topic. I had gone to the green journal (OB & GYN) website but then it locked me out. (You can only look at abstracts anyway unless you want to purchase the article. You are on your own for that.) I had some luck with the abstracts at PubMed so I have put a few here.

I decided to take a look across time…….

This first one is from 1981. . Quoted abstract from the PubMed site:

Cesarean Section for Delivery of the Second Twin

Evrard,JohnR.; Gold, Edwin M.
Obstetrics & Gynecology. 57(5):581-583, May 1981.

Four cases of combined vaginal-abdominal delivery of twins are presented, and an additional 5 cases from the recent literature are discussed. Malposition, malpresentation, and contracted cervix were the main indications for cesarean section for the birth of twin B. In the 9 cases presented, there were 2 perinatal deaths.

Interesting that this research was done during the same time frame as my experience above. I’d like to know more about those poor outcomes 😦

The next interesting article I found was researched over a 10 yr period, somewhat close to here in a larger facility, published 1997. THIS study examines the delivery of the second twin by utilizing external version vs breech extraction . 😉 The results are showing in favor of breech delivery vs version (those meeting exclusionary criteria ).. Versions were associated with higher a incidence of Cesarean and fetal distress. Neonatal outcomes no different and are stated below:

Method of delivery of the nonvertex second twin: a community hospital experience.

 Smith SJ, Zebrowitz J, Latta RA.   J Matern Fetal Med. 1997 May-Jun;6(3):146-50

Abington Memorial Hospital, Pennsylvania, USA.

The purpose of this study is to examine the incidence of cesarean section and fetal distress complicating the delivery of the second twin in vertex-nonvertex twin gestations in which the second twin underwent either breech extraction or external version. The intrapartum courses of 510 twin gestations delivered at a community hospital over a 10-year period were retrospectively analyzed. All vertex-nonvertex twin gestations were identified in which the second twin underwent attempted breech extraction or external version. Exclusion criteria included birthweight < or = 1,500 g, fetal anomaly, intrauterine demise, and monoamniotic twins. Of the 76 twin sets that met inclusion criteria, 33 underwent external version and 43 underwent primary breech extraction. The two groups had similar demographic characteristics. External version compared to breech extraction was associated with a significantly greater incidence of cesarean section (8/33 vs. 1/43, P = .008) and fetal distress (8/33 vs. 1/43, P = .008). There was no difference between groups in neonatal outcome for the second twin as measured by length of stay, 5-minute Apgar < 7, intensive care unit admissions, hyaline membrane disease, intraventricular hemorrhage, and traumatic birth injury. In conclusion, the increased incidence of cesarean section and fetal distress in patients undergoing attempted external version suggests that breech extraction may be the preferable route of delivery for the nonvertex second twin weighing more than 1,500 g

The next study was published a little later in 2001 and covered a 20 year span of time… during the 80’s and 90’s at a larger center in Nova Scotia, Canada. They noted an increase in their combination vaginal/cesarean twin births and documented some statistical data, looked at reasons for an operative second twin birth. I wish to read this study further some day to see if there is mention pertaining to mother/baby outcomes other than statistics outlined (even though that wasn’t their objective) in this abstract:

Combined Vaginal-Cesarean Delivery of Twin Pregnancies

Obstetrics & Gynecology . 98(6):1032-1037, December 2001.

Department of Obstetrics and Gynaecology, Dalhousie University, Halifax, Nova Scotia, Canada.

OBJECTIVE: To estimate the incidence and factors associated with combined vaginal-cesarean delivery in twin pregnancies. METHODS: We studied all twin births weighing 500 g or more during a 20-year period (1980-1999) at a tertiary care center. Major anomalies, monoamniotic and conjoined twins, and antepartum fetal deaths were excluded.

RESULTS: During this 20-year period, 105,987 women delivered, of whom 1565 (1.5%) had twins. Of these, 1151 twin sets fulfilled the study criteria. The mode of delivery was vaginal in 653 (56.8%), cesarean in 448 (38.9%), and vaginal-cesarean in 50 (4.3%). During the 20 years there was a statistically significant increase in combined vaginal-cesarean and elective cesarean deliveries, with a decrease in vaginal deliveries. Parity, gestational age, and birth weight discordance (>25%) were not associated with combined delivery. Compared with vaginal delivery, the nonvertex second twin was associated with a twofold higher risk of cesarean delivery (relative risk [RR] 2.3; 95% confidence interval [CI] 1.3, 3.8; P =.002); and an interdelivery interval of over 60 minutes with an eightfold higher risk (RR 8.2; CI 4.6,14.6; P <.001). Vaginal-cesarean delivery had a 22-fold higher use of general anesthesia compared with vaginal delivery (RR 21.8; CI 5.4, 88.5; P <.001). CONCLUSION: There has been a significant increase in combined vaginal-cesarean and elective cesarean deliveries among twin gestations, with a decrease in vaginal births. Vaginal-cesarean delivery is associated with nonvertex second twin and a prolonged interdelivery interval.

Now we come to 2008!  There is a study here from Texas. This study looked a twins born by C/S after labor and twins who had cesarean birth of the second twin. they campared outcomes to see if the twin of a combined delivery had more problems. The most important pieces of information I gather from this abstract of results…. (again, having NOT read the entire study):

“Combined twin delivery may be associated with endometritis and neonatal sepsis when compared with a twin delivery where both are delivered by cesarean in twin pregnancies experiencing labor. More serious neonatal sequelae, including hypoxic ischemic encephalopathy and death, were not affected by the route of delivery of the second twin.”  Hmmm 

Cesarean Delivery for the Second Twin

Alexander, James M.; Leveno, Kenneth J.; ….et al:for the Eunice Kennedy Shriver National Institute of Child Health and Human Development (NICHD) Maternal-Fetal Medicine Units Network (MFMU)   Obstetrics & Gynecology . 112(4):748-752, October 2008.

Department of Obstetrics and Gynecology, University of Texas Southwestern Medical Center at Dallas, 5323 Harry Hines Boulevard, Dallas, TX 75235-9032, USA. james.alexander@utsouthwestern.edu

OBJECTIVE: To examine maternal and infant outcomes after a vaginal delivery of twin A and a cesarean delivery of twin B, and to identify whether the second twin experienced increased short-term morbidity as part of a combined route of delivery. METHODS: Between January 1, 1999, and December 31, 2000, a prospective cohort study of all cesarean deliveries was conducted at 13 university centers. This secondary analysis was limited to women with twin gestations who experienced labor and underwent cesarean delivery. We compared outcomes of the second twin in women who had vaginal delivery of the first twin and a cesarean delivery of the second twin to those who had cesarean delivery of both twins. RESULTS: One thousand twenty-eight twin pregnancies experienced labor and underwent cesarean delivery; 179 (17%) had a combined vaginal/cesarean delivery. Gestational age at delivery was 34.6 weeks in both groups (P=.97). The rupture of membranes to delivery interval was longer in the combined group (3.2 compared with 2.3 hours, P<.001). Endometritis and culture-proven sepsis in the second twin were more common in the combined group, respectively (n=24, odds ratio 1.6, 95% confidence interval, 1.0-2.7; n=15, odds ratio 1.8, 95% confidence interval, 1.0-3.4). These differences were not significant after logistic regression analysis. There were no statistically significant differences in an arterial cord pH of less than 7.0, Apgar score less than or equal to 3 at 5 minutes, seizures, grade III or IV intraventricular hemorrhage, hypoxic ischemic encephalopathy, or neonatal death. CONCLUSION: Combined twin delivery may be associated with endometritis and neonatal sepsis when compared with a twin delivery where both are delivered by cesarean in twin pregnancies experiencing labor. More serious neonatal sequelae, including hypoxic ischemic encephalopathy and death, were not affected by the route of delivery of the second twin.

I gather from these studies that a combined delivery route leads to more problems.. however…there are probably more problems than breech presentation alone to lead the provider to make that choice. I believe that many newer providers of obstetrics in a hospital setting are more apt to do a scheduled C/S for any vertex-nonvertex twins they encounter. That is what is done in my facility today. The same for all breech presentation singleton gestation.

Where is that old-fashioned nurse when you need her?? How ’bout the old fashoined doc??? 😉

I am very interested in anyone’s story or experience either in healthcare or your personal birth. Please let me know if you know anything about this!

Thanks for reading!

Watch Wednesday ~ WAIT to Clamp Cord!

Watch the video Wednesday

Just read an awesome Post about Delayed Cord Clamping by a fellow Labor and Delivery Nurse who has an excellent blog you should all read. I have a link to it on the right hand side… “nursingbirth”.

She did tremendous research and has supplied fabulous information. 

Here’s a shout out to you nursingbirth!!

Watch this video..