Skip to content

Prescription and Herbal Galactogogues

033


Gotta make more milk!

I have compiled a literature search of the most common presription drugs and natural or herbal galactogoues used for low milk supply.

Check out my comprehensive guest post over at Breastfeeding Mom’s Unite here! I would love for you to visit her awesome site and leave a comment for her (and me)!

Thanks!

Initial Low Milk Supply: A Breastfeeding Story – Case Study

034     The History:

 One typical busy morning coming on shift, one of the couplets I received report on was a 3 day post-op C/S mom and baby who were scheduled for discharge this same morning.  She had been a long 3 or 4 day failed attempt to induce a vaginal delivery for fetal macrosomia (big baby) at 40 5/7 weeks before the C/S.  Lots of IV’s, lots of Pitocin… all before the birth.

Her baby weighed 10 lbs 4 oz at birth. We got in report that his glucose sticks had all been over 60 initially so they were stopped early on. His exams were normal.  His total bilirubin this AM was 11.3 at over 72 hours of age. He was “breastfeeding only”  (*sigh*from the nurse giving me report).  She then expressed a concern that  he was down 10% from birth weight weighing 9 lbs 4.5 oz today.  When I asked her about the feedings, she said he’s been nursing beautifully all the time but nobody’s had time to stay in the room and watch him feed. I asked about the output and she reported he’s been voiding, the last stool was a couple shifts ago.  Then the nurse added “We told her you were here today, Melissa, she has a lot of questions for you. ”

I was able to juggle some things around, have staff cover some of my other responsibilities temporarily to make this a priority. Since I am a general staff nurse, there are often more pressing situations. Fortunately, today I was able to manage the time to see her right away.

I went in and introduced myself to Meg*, Brad* and their son Mikey* (*names changed). They had indeed been waiting for me.  Breakfast was underway and Mikey was asleep in his crib. I asked her a few general questions in a relaxed manner about breastfeeding first to try to establish some background: Mikey’s energy level, drinking pattern, feeding frequency, and diaper checks.  It is important to gather information and observe the feeding  in the process of  a full evaluation to determine adequacy of feedings.  The information I got was concerning.  He spends a lot of time at the breast, falls asleep quickly, not very energetic with every feed, not much change in her breasts at this point and no stool since yesterday. I did not tell her I was concerned at this point, nor did I mention the weight yet. I asked if I could check him now and if  it would be alright if I observed the next feeding.. We determined that should be with in the next hour. I talked about feeding cues and asked her to get me if  Mikey seemed ready to eat before I came back.  His vital signs were normal, jaundice not too significant for his age, diaper contained a small amt concentrated urine, and Mikey went immediately back to sleep.  I felt he was OK at the moment and needed to go do a few other  things with other patients.
 
At this point I am feeling pulled in different directions because Meg’s situation could easily take hours of my already busy morning. I am upset that this has possibly been going on the last 3 days and hasn’t been evaluated properly, now it’s day of discharge! How do you do the proper evaluation, give the needed gentle support, make possible feeding plan arrangements in fragments of time? This is what I am trying to change…in my opinion, we the hospital, helped contribute to this situation of possible inadequate feeding and supply… we need to help her! I talk to the charge nurse and it’s cleared to keep my coverage the rest of the morning.. good thing L&D was quiet!
 
Mikey’s doctor comes in and thankfully it is a partner who is very pro breastfeeding and open minded to try options a mom may choose. I gave her report on his physical status, VS, weight, earlier glucoses, and the Bilirubin. I summed up my plan to evaluate feeding quality but suspected he has been ineffective at the breast & milk supply/production may be delayed. I added that I was going to check his glucose if he had low energy level, and encourage pumping or expression for the mom and get that milk into the baby as well as encouraging her to stay for a few feedings to work with me. The MD was happy with these ideas but requested he be supplemented (complemented) with formula at all feedings now until his weight came up. She supports the theory (as I do) that the birth weight can be somewhat inflated with all the pre-birth IV fluids mom rec’d and some of what he lost may be fluid.  The MD said that if things were better by afternoon, he could go home. She went out to examine him at mom’s bedside.
 
I went in for my feeding observation a little while later. Meg now knows his total weight loss and feels very upset. I give her a lot of support and agree with the doctor that some of that could be fluid. I then find out..Meg is an RN here at my hospital on another floor! It had not come up in conversation! So now I know she is even more worried because we nurses always think the worst! I do my best to think simple and encourage her to do the same… it is very early and we can turn this around quickly with a strong approach.
 
My Evaluation:
  • Good independent maternal positioning, holding and offering of the breast
  • Nipples erectile, breast tissue soft, pliable, small amts colostrum expressed–> mom reports her breasts were “swollen first 2 days”
  • Latch fairly adequate but not optimal-> improved greatly with football position and instruction on asymmetrical latch approach (I’d like to say here that I have a” if it’s not broke don’t fix it” attitude. I don’t correct a latch for a mom who has no pain and good milk transfer, we talk about it in case it may come up for though)
  • Mikey very sleepy at breast, difficult to maintain latch, no milk transfer observed–>breast massage during feed tried without improvement
  • Due to continued low energy level (suspected caloric deprived state causing sleepy ineffective feeding behaviors) a bedside glucose was checked. Result was 49.
  • Diaper dry–> the previous concentrated void was only his 2nd in last 24 hrs No stool last 20 hrs and that one was dark.
The mother’s feeding plan:
Many options and teaching points discussed with Meg including the need to boost caloric intake –>starting right now, methods to get her milk or formula into the baby avoiding bottles, a vigorous pumping plan to augment breast stimulation, alternate breast massage, how to observe for swallowing and milk transfer at the breast etc.. I also discussed with her how in my experience, sometimes it is like magic once the baby regains up to birth weight… they just take off!
She chose:
  • Cup feed formula now while she pumped –>Mikey would not cup feed so we used a syringe, 18 cc, repeat glucose 62
  • Pumping round the clock, double pumping –> Meg rented a hospital grade pump for home use
  • Keep close eye on feeding cues, put Mikey to breast in football w/ latch process discussed earlier
  • Closely watch signs for milk transfer, correct feeding activity while at breast, sucking rythym 1 or 2 sucks /swallow ( Brad was very involved in this process of learning the observation techniques)
  • Use breast massage/ compression while baby @ breast through feed to increase milk transfer
  • Goal of min 8 effective feeds in 24 hr..wanted to try for 10 –>agreed to feed expressed milk or formula 1/2 to 1 oz after each feed first 24 hrs until re-weighed next day
  • Have as 1st 24 hr goal:  to see 3 -4 increasingly wet/clearer diapers and at least 2-3 good sized stools
  • Return to MD for F/U bili and wgt check next day
  • Call IBCLC for eval in next few days if weight not adequate and not independently breastfeeding/output  within safe parameters for age

The follow up reports:

  • DAY 1 (In hospital) Mikey fed 3 more times in the hospital at 2 hour intervals.  Each time he had about 15 to 20 cc of formula by syringe. Each feed was improved but not adequate quality of milk transfer. Meg pumped 4 times before discharge not getting much first 3 times but 4th time she got almost 10 cc! Mikey had 1 conc wet diaper and a med sized dark stool. We re-weighed Mikey prior to discharge and he was 9 lbs 5.5 oz.  Meg left the hospital late that afternoon while I had been called to a STAT C/S. She was determined to go home after all the time she had been there! I called her later and she was on target with her plan.
  • DAY 2 (first 24 hrs home) Seen at Peds office. (reported to me from MD)  Bilirubin 10.6, weight–> 9 lbs 7.5 oz! Baby more energetic, better quality feeds reported. Meg still power pumping, now getting 1 -2 oz per pumping and giving to baby with syringe and only used formula occassionally if no breastmilk.  Had 3 wet and 2 stools since discharge, stools lighter in color. MD arranged F/U weight visit for 2 days, will arrange IBCLC if no strong improvement before 2 more days
  • AGE 6 1/2 days Seen at Peds office. (reported to me from MD) Weight–> 9 lbs 11 oz !!! Meg having fairly same routine but not always pumping if she feels Mikey had good milk transfer. She reported increased  breast fullness, 6 wetter, lighter urines and 4 mostly yellow stools in each of the previous 24 hr periods.
  • AGE 2 weeks  I don’t have MD office reports but Meg called me to tell me Mikey was 1o lbs 7 oz at his 2 week check up and nursing a lot better EVERY feeding!! She was still attached to her pump, gradually decreasing the sessions, just felt safer to keep going with that. If she gets milk she was still giving it to him. This was her security blanket and she was happy doing it. She was very proud of herself and crying happy tears! 🙂

Meg’s case was a beautiful example of HOW a situation can turn around quickly.  An individual mother’s determination coupled with a productive plan can produce these results. All situations are different.

Every mother and baby deserve our best!

Not your Usual Birth Plan

002


A birth plan is usually a written plan from the mother to her caregivers describing her wishes, what type of options she’d like to take advantage of, things she would like to happen thru out her labor and birth, what things are important to her as she experiences birth.  There are various resources out there to help a new mom explore options and formulate a plan.. especially for a hospital birth.  It is important that the mom review this with ALL her care providers AND especially the L&D nurses…. the advocates who help you actually realize the goals with in your plan. I have a fellow L&D nurse blogger who has done extensive research on the topic and wrote a 2 part series on Writing Your Birth Plan- Tips from an L&D Nurse over at nursingbirth. I would highly recommend you check it out especially if you plan on a hospital birth.

Many times these birth plans accompany a mom’s prenatal chart weeks in advance of her birth. Over the years there has been a gradual acceptance of the plans in my facility where historically, there had been much resistance for the mother’s input what so ever.  Much like the attitudes towards homebirth…. The doctors or nurses would casually peruse the plan then toss it aside and have a good laugh…. saying…. ” oh- she’ll end up a section for sure!”  Unfortunately, they were often right about that– many of those early birthplans never seemed to go as mom wanted, giving the staff fodder for snide comments and remarks. Sad but true. 😦

Recently, we recieved a birth plan that was not at all like any other.  Maybe some of you have seen plans like this… maybe some of you actually wished for births like this…. Hey~ who am I to judge? …. I am only here to help,  it isn’t my birth.

Her Birth Plan requested:

  • Pain medication as soon as possible….. I prefer to have an epidural as soon as possible
  • Please do not try to make me have breathing patterns through contractions… I’m afraid I’ll be too nervous
  • If a Cesearean is needed, please put me to sleep
  • I want only my mother with me in the labor and delivery of my baby
  • When the baby is born, I do NOT want to touch him until you clean him off
  • You can do his eye ointment and Vitamin shot, bath and all procedures before I hold him
  • I want to hold him wrapped in a blanket, not skin to skin
  • I want the baby to be in the nursery as much as possible at night so I can rest
  • I want to feed my baby formula from a bottle. I don’t want to breast-feed
  • I want to stay in the hospital for the whole allotted time so I can rest

My first thoughts were… Sweetheart, you could have ALL THIS without even asking!” ……..

Sadly, despite all efforts to improve,  …  things still happen exactly like this for many births.  We just don’t usually see it written out as a formal request or plan!  At least this is how this mother wanted things to happen.

This little mommy came in and delivered vaginally. Her plan was very easily carried out. 😉  I am very happy to report that she and her son were healthy and she displayed very postive interaction with him. Very loving and caring. She was very very happy with her birth and with being a mother!

That is all that really matters in the end.  Options– and what you as an individual would like to have for your birth. How much education she had before chosing these options… I’ll never know.

 Now I am asking the rest of cyberspace world.. have you ever seen birth plans like this???

A Formula Rep turned my Maternity Leave Injury into a new career as an IBCLC? Really?

matleavecarnivalbox

My contribution to this fabulous Carnival of Maternity Leave  , is a story of how during my maternity leave, an injury occurred leading to a career change specializing in Lactation… ! It starts with the birth of my third and last baby…… A  girl….. (after 2 boys) was also born by C-Section.. a first for me.

Well– first, let  me back up a few years… I’ve had a potpourri of maternity leaves. I have been a Maternity/L&D/Nursery since the mid 70’s.  I always worked full time and had never entertained thoughts of staying home with my children once they were born because the USA didn’t assist in providing any type of viable option for families who rely on two incomes or single moms with one income.  Prior to FMLA,  maternity leave was pretty much up to the employer as far as I understand it. The USA doesn’t offer any paid leave (unless offered by individual employer). For my first baby in 1979- I took 7 .5 weeks and went to a weekend 12 hr shift job which at least allowed me 5 days each week with him. 

 When my next baby was born in 1985, I worked at the same facility I am now. We were allowed to save up ALL Vacation, Holiday, and Sick time to be used collectively with your hospital allowed 12 weeks off.  I was able to have 5 1/2 months total, partially paid time to be with my new baby. Since he had to have surgery at 3 months, I needed that time and could have used more.. My leave was actually supposed to end on Christmas day (YUK).. however, they graciously allowed me to come back on the 26th… also his first day in Day Care. 😦

So back to my third baby in 1988~I had had a C/S — (that’s another story).  I had to be hospitalized for 10 days after the surgery with a whopping infection. A fresh incision and chills with a temp of 103.8 do not go well together! [Nurse Curse] Anyway, I made it thru–> healed and returned to life as a mother of three. The same type of collective accumulated paid hours were allowed withthe hospital’s offered 12 weeks. I didn’t have as many hours saved up as last time but was hoping for the best length of time.  One day in church, I held my little 2 month old baby girl on my shoulder with one hand, while using the other to hold the hand of my active 3 yr old boy as we made our way down the aisle. Suddenly, my boy squealed with delight and whipped over in a different direction. I held my daughter and did a sudden twist and reach for my son as he squirmed away. I immediately felt something “give” in my back.

It took a few days for me to feel the true extent of the injury. I thought it was just a little pulled muscle. After a 5 hour drive to my sister’s for a family visit, I ended up writhing on the floor with the unstoppable intractable “fire hot poker” pain of full blown sciatica…. all down my right side. I had to go to the hospital ER away from home, unfamiliar doctors, for help and drugs! Boy, I needed relief. As explained to me by the doctors… this was not the same as sciatica from many other causes. This was a swollen inflamed sciatic nerve… we didn’t know why yet.  The only thing helping at that point was medication and ice.. a lot of ice. I still insisted they give me meds I could take while breastfeeding, so they weren’t too strong.

I got home, went thru an MRI and diagnostic process, different doc’s, different opinions. I had a disc “blow-out” with”free extruded disc fragments” at L5-S1. Some felt surgery was needed immediately, others said to wait.  After careful consideration, we decided to wait and do some conservative type treatments with oral and epidural steroids. I still had to heal well enough to work, though. I spent many nights crying and wondering HOW I could work ??? How could I go and be on duty…running all over to keep up with the pace, helping people thrulabor and delivery…respond to emergencies…how?? I could barely care for my family! I called many friends while I was on periods of bed-rest and had various treatments during the time I had left of maternity leave. (I eventually did have to extend the leave a couple weeks for more recovery. I ended up witha 5 month leave altogether). I was searching for ideas.. visions of something less physically taxing which could combine my knowledge of labor/delivery/postpartum and neonatal care….. and allow me to continue working. I was, after all, the major bread-winner in our family!

Finally, a friend came up with an idea. He was actually a formula and drug rep for Ross labs.. TRUE!! But he was a friend, had heard I was hurt and stopped by the house to see how I was. He was a rep to many hospitals in the NorthEast and had exposure to what else was going on– what other hospitals were doing.  This was 1988, only a few years after the emergence of the Lactation Consultant profession. I had never heard of it. Sometimes word traveled slowly (by pony express) and things changed slowly in my little neck of the woods. He encouraged me to check it out and gave me phone numbers of LC’s at some of his other hospitals. I was really excited! I called a few and found out more about the lactation profession and the relatively new Board exam given every year in July to gain the credential of IBCLC.  I was actually naiveenough to think I could take the exam with my current knowledge base!  HA! (Unfortunately, this is what many nurses with a little experience think…we think we already know it all! Ha!) 

I called one of the LC’s at a hospital not too far from me. We talked a while and I had my eyes opened as to the extensive and vast knowledge base needed to become a lactation professional. I launched a quest for the best way to gain this knowledge. I joined LLL and went to meetings. I made home visits with the local LLL leader. I wrote many letters, made many phone calls searching for some type of education program. (remember– no Internet back then!)

Finally I found the perfect program for me. There was a correspondence course offered to be done all through the mail and phone calls designed to be an 18 month course.  It was a Lactation Consultant Course offered by BSC Breastfeeding Support Consultants! (the link shown is for their current course) Back then, you could be called a Certified Lactation Consultant after completing the clinical practicum and final exam. Because of continued back problems, I started this course in early 1989, had to take a few months leave from the course and completed it in early 1991. I then went on to continue studying and sat for the IBLCE exam in 1993 earning  my IBCLC status!

I have always continued to work as a staff nurse. I found a corset style back brace and found the best balance possible between family, back pain, work and more pain. I was able to get the pain subdued with steroids to carry on with life. In 1992, during a particularly gruesome relapse, I eventually consented to a myleogram… something I had previously NOT wanted. They also did a CT scan while the dye was in place. These tests showed my right Sciatic nerve had been pushed way up out of place by the disc material. I consented to surgery by a fabulous neurosurgeon the very next day. It turns out, the disc was actually adhered to my sciatic nerve!! He had to meticulously excise it off the nerve!!  My post-op pain was minimal compared to the pain I had before surgery. I was able to go back to full duty in 8 weeks!

Over 20 years later, I am still working as a staff nurse and am now a CLC… Certified Lactation Counselor.  Becoming a breastfeeding professional has enhanced and fortified my life! I am immensely happy I have gone down this road. To think it all came about as a suggestion from a Formula Rep!?!?!

Hope all had a great WBW 2009!!


Hope all had a great WBW 2009!!

WBW~ Breastfeeding in a Personal Disaster…. C.Michael’s Story

SendPicture14 August 2nd…..Today is my son’s 24th birthday. Yeah…I’m old 😉 This is not really the theme of WBW but I will take this opportunity to tell his breastfeeding story on his birthday.

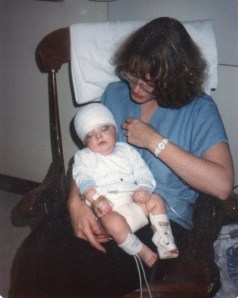
In 1985, I gave birth to my second son. C. Michael. He was 37 weeks and behaved like many     near term babies… Breastfeeding got off to a slightly delayed start but then was awesome and without problems! Yay!

I wish C. Michael’s physical health was the same way.

C.M. was born with craniosynostosis.  Specifically, saggital craniosynostosis. Infants skull bones are purposely NOT fused together at the time of birth so the head can mold as baby makes his way down the birth canal and into the world. The different skull bones will overlap easily along the suture line so as to fit thru the pelvis. These bones then gradually reshape and the sutures eventually fuse.

My son’s saggital suture line was prematurely fused…causing a misshappen head. When there is a premature fusion, the growth can only occur parallel to the fusion. The saggital suture goes from the anterior fontanel along the top of the head to the posterior fontanel. Parallel growth would cause his head to be really oblong, or football shaped.

We took him to 5 doctors to decide if we would have corrective surgery… Yes that’s right…. it had to be OUR decision. Although this is a birth defect and causes a visual deformity, it does NOT affect healthy brain function UNLESS there is fusion of more than one suture and growth is impeded. So it is cosmetic surgery.

We decided to go ahead with the surgery at age 3 months and had everything arranged at CHOP (Children’s Hospital of Philadelphia). The craniofacial team was amazingly supportive. I was so very scared. My husband and I could not sleep. I hadn’t been able to sleep well since he was diagnosed. How many new mom’s tell you the baby is sleeping but they can’t sleep??? I’m not going to get into the whole surgical procedure… but the  main point of this story is how breastfeeding not only provided C.M. with the best nutrition and immune system protection, it also saved me thru my son’s ordeal.  My husband was able to pre-donate blood so we both felt like we were doing everything physically possible as his parents to help him tolerate and recover from this major surgery.

I was so pleased to be able to sleep right next to him in the hospital. We had to go in the night before and the he was not allowed anything after 4 am… he could nurse up to that point. I woke him to nurse around 3 am. It was very bittersweet. I was crying and he was happily nursing, not know what was coming next. It was difficult just to see the IV placed, let alone the actual surgery.  I was so grateful and happy they had done alot of pre-op procedures the night before when I could nurse him after each study. Now , when they wheeled him off to the OR, I was almost happy he had been slightly sedated because as hard as it was, I could never have handled him screaming at that point.

While he had the surgery, I headed first to the pumping room to try and get as much milk stored as possible. I had not been able to pump well before this so I had limited expectations. It was the first time I had used a hospital grade pump so I had much better volume than I expected. I stored a couple bottles and was feeling actively involved in his recovery already!

They called us to meet him outside of recovery a couple hours later. It was very difficult to see his head swollen and heavily bandaged. He had had a blood transfusion once already in the OR and they expected he would need more. Apparently the bone edges ooze when cut.  We took turns with him until he wasn’t groggy any more, then, once awake…. I rarely left him.  I was told he had to have a little bit of an electrolyte solution in a bottle first before I could nurse him, just to make sure he didn’t vomit.  He was ready to nurse in about another hour. They took him out of the crib, with his massive head bandage, black and blue eyes and 2 IV lines….place him in my arms and we gently rocked and nursed.SendPicture12

I felt completely lost, even as a nurse or especially as a nurse…. because seeing your child like that is very difficult. I kept thinking all the worst possible complications would happen to him. I wanted to keep him safe, protect him. I struggled with tremendous guilt, thinking I must have done something to cause this to happen… It must have been my fault.  Many parents go thru that, I’m sure. Breastfeeding him thru the hospitalization, two more blood transfusions and recovery period helped me feel like I was actively healing him. My husband felt similar thoughts because they used his blood for the first 2 transfusions. It was an empowering feeling.

I’ll close by saying that finally being finished with the decision process, the surgery completed (sucessfully I’m happy to say) and on the recovery road also cured my sleeplessness.

The night nurses at CHOP laughed at me! There I was, sleeping right next to my precious brave 3 month old post-op son…and they had to wake me up to tell me he was crying to feed in the night.  😉

What a handsome guy now!

What a handsome guy now!

logo_01

August is here! World Breastfeeding Week Aug 1-7

World Breastfeeding Week

WBW Theme Logo 2009

WBW Theme Logo 2009

WBW Theme for 2009
Breastfeeding: A Vital Emergency Response
Are you ready?

OBJECTIVES OF WORLD BREASTFEEDING WEEK 2009

  • To draw attention to the vital role that breastfeeding plays in emergencies worldwide.
  • To stress the need for active protection and support of breastfeeding before and during emergencies.
  • To inform mothers, breastfeeding advocates, communities, health professionals, governments, aid agencies, donors, and the media on how they can actively support breastfeeding before and during an emergency.
  • To mobilie action and nurture networking and collaboration between those with breastfeeding skills and those involved in emergency response.

RATIONALE

  • Children are the most vulnerable in emergencies – child mortality can soar from 2 to 70 times higher than average due to diarrhoea, respiratory illness and malnutrition.
  • Breastfeeding is a life saving intervention and protection is greatest for the youngest infants. Even in non-emergency settings, non-breastfed babies under 2 months of age are six times more likely to die.
  • Emergencies can happen anywhere in the world. Emergencies destroy what is ‘normal,’ leaving caregivers struggling to cope and infants vulnerable to disease and death.
  • During emergencies, mothers need active support to continue or re-establish breastfeeding.
  • Emergency preparedness is vital. Supporting breastfeeding in non-emergency settings will strengthen mothers’ capacity to cope in an emergency.

Source: http://worldbreastfeedingweek.org/

What we are doing…….

At my facility we are working on action plans to include breastfeeding support in our exisiting disaster response plans. We are never immune to disaster…. we just had a tornado here on July 29th with a lot of damage, small flooding and many homes with loss of power and clean water.

We are promoting WBW with staff and physician education as well as small gifts to new moms congratulating them on their decision to breastfeed!

WHAT ARE YOU DOING???? I really would love to hear your stories and your efforts so that we can share ideas.

Wordless Wednesday.. Severe Storms forced more “ME” Time….really

My front porch~ still raining lightly

My front porch~ still raining lightly

Taken at the same time with a flash

Taken at the same time with a flash


I had a fairly productive morning and had plans to do a lot of computor work this afternoon….. I had NOT intended to hang around with more “ME” time today… really!

We’ve had a day of severe Thunderstorms and an unconfirmed TORNADO about 7 miles from my house. Reports of blown off roofs/barns leveled and unconfirmed~ one person missing….. We are certainly hoping everyone is alright. My power was out for 5 hours.  It just came back on.

In the meantime… what could I do???  I took advantage of the natural light, enjoyed a very good book on my front porch when the rain wasn’t so intense…with my very scared Chocolate Lab…Joey.. (Sir Joseph Clay Augustine of Belmont)….I can’t think of a better companion to hang with since my children are not around….


I just heard more thunder mommie...

I just heard more thunder mommie...


I know it was THUNDER mom...

I know it was THUNDER mom...

And practice a little photography~
 
Rain glistening in the pines...

Rain glistening in the pines...

More rain in the pines

More rain in the pines


Mama needs “ME” time…. How do you guys do it all?

Birth and Breastfeeding Blog? I haven’t been doing much blogging.. Hmmmm……I feel somewhat guilty…….I mean I feel like I have a lot going on in my life… but ~

I don’t have small children….. mine are grown and gone… for the most part.

I don’t work 5 days a week….I work 3..but they are 12 hour shifts

I barely cook… at least no really complicated meals… I’m not a crunchy (didn’t even know what that word meant) organic earthy person.. I try to eat well but — the easier, the better…or frozen 😉 is ok with me!

I don’t scrub-clean my house….. I like things orderly so I straighten, manage the dishwasher, blow the dust off frequently used areas, but hey, I gotta clean the bathroom.. that’s a must.

My husband does all my floors and his own laundry….. everyone in my house has always done their own laundry. My husband is just NOT a needy guy at all! He’s my dreamboat.

I’m not really married to my work… so to speak — but I’ve always taught my family that I have to care for people all day long at work…so they need to be independent where they can and help care for all their own needs. Mama is always available for the important stuff or talks.

Mama simply needs “ME” time..and a lot of it! It renews my spirit and rejuvenates my energy. Sometimes I feel like a selfish be-otch.. but I KNOW I need it. I’m worse with out it.

Today I worked on several work projects here at home…  Some PowerPoint, outlines for projects in my Clinical Expert Applicant Curriculum…. Specifically on Evidence-Based Practice and research;  Project participation within my organization… (searching for compelling ideas to stir up others enthusiasm); Community involvement; Cultural Diversity; Service Excellence and Preceptor/Mentoring of new nurses. Just a little somethin-somethin.

Oh and I forgot to mention a little thing called.. WORLD BREASTFEEDING WEEK !!   August 1-7  (more on that very soon)

A lot of the blogs I read contain regular well researched posts. I have over a hundred posts still to read in my reader! I want to tell my stories but I don’t always have the energy to figure out ways to tell the essence of the story and change enough to protect the identities.

So I do a lot of thinking and dreaming about what I’ll write on this blog — without really writing. Don’t give up on me yet.    If you are looking for something really cool or inspiring..I have it inside me head.. I do… it’s in there — still waiting to be gracefully typed with two fingers….

BUT

I’m probably watching a movie, reading a book or going out to lunch.
Fellow Bloggers… How do you pour it out on to the pages? I have a fairy tale impression of you all.

JUST HOW do you guys do it all?? Come clean with me.. are you all magical self-less supermom wizards?

HomeBirth Transfer~ Doc says NO to C/S~

I wrote a few stories a few weeks ago because I was proud of my hospital that week– sorry I didn’t finish the stories until now……

iStock_000004564778Small

~She lived about 8 -10 miles outside of town. “Ellie” was having her first baby at age 32.  First baby, first pregnancy, no risk factors…. an easy uncomplicated pregnancy. She had done some research, not extensively, judging from some of my conversations with her and her husband…but she knew what she wanted. She had made a beautiful plan with a CPM for a water tub home birth. This particular midwife has been doing home-births in my area for a long time.. (She was the one cowering in the L&D hallway in this story…). The story of how things progressed up to transfer to the hospital was told to us by both the mother, father and midwife. 

~Her labor started with regular contractions at 39 weeks. They progressed from early labor which lasted around 6 hours to a more active labor with contractions about every 2- 3 minutes.  Her cervix had dilated to 6-7 cm. This pattern of contractions continued for hours. Ellie was in and out of the tub, walking, dozing, in and out of the shower, squatting, doing many different position changes throughout the next 6 to 8 hours. When she was re-examined by her midwife, she had made no cervical change in all that time. This can happen sometimes, things can stall out and pick back up again. Ellie reported that the contractions may not have been as strong at that, so she wanted to wait it out, maybe nap. The baby’s heart rate checks were all good.

~Everyone rested about 2 hours … Ellie’s water broke (clear fluid)  about 1 am and her contractions got more intense. The CPM checked her cervix about 3 am and felt no change. She still was 6 -7 cm dilated and the head was at about -2 station. The midwife then brought up the idea of possibly transferring to the hospital. Ellie said NO! Is my baby alright? “Yes….” said her midwife.. “Then No..I’m staying here, — I can do this.”

~Back to the tub… In and out of the shower, total body massages.. contraction pattern the same with increased intensity…next cervix check at 730 am… still 6-7 cm. Now Ellie was tired. Really tired. Exhausted! The baby was great on all checks. Her midwife again brought up the transfer to hospital idea, talked to her about the possibilities of pitocin, epidural etc… Ellie was now wanting anything, agreeing with anything–to get this over with.

~She arrived at the hospital around 8- 830 am very upset. Her husband and midwife were with her and her CPM had all her prenatal care info. Some of the first words out of Ellie’s mouth were that she wanted an epidural and a Cesarean! The nurses on duty this morning were awesome! They calmed her down, had her hooked up to the fetal monitor and observed her contraction pattern and the fetal heart rate pattern response. The baby looked excellent! The midwife and hubby coached her through the contractions while the nurses gathered their admission data.  The doctor checked her and she was still about 6-7,  swelling of the cervix noted, about -1 station. Ellie asked him if he would please do a C/S and he said no… (yeah!).  He said that he felt the best option at this time was to do the epidural she was asking for and observe her contraction pattern… possibly add Pitocin. He talked to her so nicely and non-judgmentally. Many of the other docs would have taken her right into the OR with very little discussion of options. She had been 6-7 cm dilated for some approximate 16 hours.

~After the epidural, Ellie and her husband and midwife all slept. The doc did NOT start pitocin right away, he said that she may need to rest and the contraction pattern couldstart to become of better quality once she rested and was better relaxed. WOW! Where did this guy come from? I’m so amazed and happy and quite frankly, shocked. This was a newer OB here.. I wanted to ask him where he’d been all my life! I went in to talk to Ellie and introduced myself. I told her I was so sorry thingsweren’t progressing the way she had hoped and sorry she didn’t get to stay home. She thanked me and said at this point, she was ready for it to be over! I told her she was really quite fortunate to have this particular doctor on duty today. Except for one bad apple from the night shift just leaving when Ellie arrived, everyone was wonderfully supportive and accommodating. Ellie’s contractions indeed did start up in a better intensity pattern on their own….. however their continued to be a lack of progress.  Once again, she asked the doctor to get it over with now and please do a C/S. 

~The doctor said NO again! He explained that her uterus was probably tired and the quality/intensity of contractions just may not be what was needed for the job to get done. He explained that the fetal heart rate tracing was beautiful and her membranes had been ruptured less than 12 hours. No baby risks…  He felt it possible the baby merely needed to get in better position and the contraction quality needed to improve.. and then he would re-evaluate. Ellie agreed with renewed optimism. The pitocin drip was started. She didn’t need much before the contraction pattern got much stronger, longer and better quality.  He came to re-evaluate her only after these better contractions had been consistent for 2 hours. The vaginal exam revealed the cervix was the same ..still the same and possibly more swollen.  He said he felt the head was not as well applied to the cervix as it had been.. but still at -1 station. He examined her with and without a contraction. Same in his opinion. Ellie lost all her fight. Her support people rallied to help her, but she was now insistent.

~This time the doctor  said she certainly had reason to feel this way, had given this a great try. He told her he still felt she could try longer… that we could alter positions with the pitocin, keep her comfortable with the epidural and keep going… the baby was handling all this just fine. He did say that there was a possibility the baby had his head in a tilted position making it difficult to descend the birth canal. He then let it up to her and told her if she wanted the C/S, he would do it at this point.

~YES I want a C/S! Ellie exclaimed. We did the C/S about 3 pm… some 7 hours after transfer and approximatelyclose to 24 hours of being 6-7cm dilated. Her gorgeous 7 lb baby boy was delivered operatively with apgar scores of 9 and 9. Pink and vigorous! Beautiful. I was able to get him skin to skin in the OR.. that was one of the first times all the players didn’t object and I went with it! (It won’t be the last….and next I’m trying for breastfeeding on the OR table!) Upon delivery, the OB noted the baby had been acynclitic . This is when the head is tilted to the side, ear towards the shoulder.  It is probably responsible for her long stall in labor. The OB still felt she could have delivered vaginally given time and good management. I am just so happy he was there.  I am proud of this mom, her partner and midwife and of our whole team! This mom was able to make good educated choices about her care despite dealing with the stress of a transfer.. and was able to feel so very very proud of how hard she tried.

In the end it was her…… who gave in to the C/S … not her doctor. 

Of that we can be proud

🙂

At the beach !!!

Humpback WhaleI’ll be away and offline …on vacation at a Connecticut Beach House until after the 12th.

Later…………